

Substance use disorder billing runs on the level of care a payer agreed to buy: outpatient, intensive outpatient, partial hospitalization, residential or withdrawal management. Each level has its own code set, its own authorization language and its own documentation burden. This service line also carries a federal confidentiality rule that no other behavioral health service carries.
Substance use disorder billing starts with the level the payer bought
A payer buys a level of care. The diagnosis supports the claim, but the level decides the benefit, the code and the review. An office visit, a structured evening program and a 24-hour residential stay sit in different benefit categories, each with its own authorization language and its own documentation test.
The continuum most plans and providers use is published by the American Society of Addiction Medicine, which owns and licenses The ASAM Criteria. Its fourth edition organizes treatment into four broad levels, from outpatient through residential to medically managed inpatient, with decimal levels marking intensity inside each one. It is copyrighted, so this article names it rather than reproducing it.
| Level of care | Code that signals it | What the plan buys | Authorization |
|---|---|---|---|
| Outpatient (ASAM 1) | E/M or psychotherapy code, place of service 11 | Individual visits, medication management | Usually none |
| Intensive outpatient (ASAM 2.1) | H0015, or revenue code 0906 | At least 3 hours a day, 3 days a week | Notification or authorization |
| Partial hospitalization (ASAM 2.5) | H0035 or S0201, revenue codes 0911 to 0913 | A day program, often 20 or more hours a week | Prior authorization |
| Residential (ASAM 3) | H0017, H0018, H0019 or H2036, per diem | 24-hour care, without room and board on H0017 | Authorization before admission |
| Withdrawal management | H0010, H0011, H0012, H0013 or H0014 | Medically managed withdrawal | Authorization or 48-hour notice |
The level is a set of service hours and staffing requirements the plan can audit, not a label the chart carries. A program billing H0015 has to show that it operated at least 3 hours a day and 3 days a week, because that is what the code says the program is. An authorization, in turn, is written for a level and a span of days or sessions.
The Medicare benefit that pays for medication in an opioid treatment program
Medicare Part B pays an opioid treatment program with a bundled payment built on weekly episodes of care, a benefit that began January 1, 2020. To bill it, the program must be enrolled in Medicare, certified by SAMHSA, accredited and holding a provider agreement. There is no patient copayment, and the Part B deductible applies.
The threshold to bill a full episode is one service. If any drug or non-drug service was furnished during the seven-day episode, the matching weekly bundle can be billed. A week with no medication but at least one non-drug service bills G2074, the bundle without the drug. Only the enrolled program can bill these codes.
| Code | What it covers | Medicare frequency ceiling |
|---|---|---|
| G2067 | Methadone weekly bundle | Once per 7-day episode |
| G2068 | Oral buprenorphine weekly bundle | Once per 7-day episode |
| G2069 | Injectable buprenorphine weekly bundle | Once per episode, no more than every 4 weeks |
| G2073 | Injectable naltrexone weekly bundle | Once per episode, no more than every 4 weeks |
| G2074 | Weekly bundle with no drug furnished | Once per 7-day episode |
| G2076 | Intake activities, add-on | New patients starting treatment only |
| G2078 | Take-home methadone supply, add-on | Up to 7 days, units up to 3, only with G2067 |
| G2079 | Take-home oral buprenorphine, add-on | Up to 7 days, units up to 3, only with G2068 |
| G0137 | Intensive outpatient services, add-on | Only with 9 or more services and 9 hours a week |
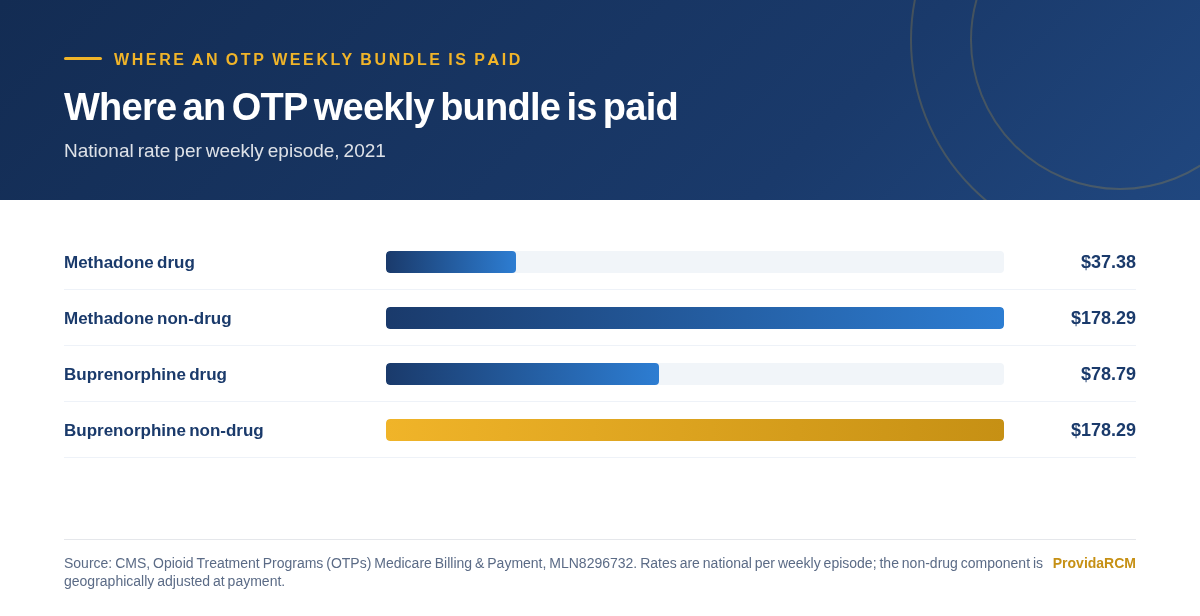
What Medicare pays for each program service
Source: CMS, Opioid Treatment Programs (OTPs) Medicare Billing & Payment, MLN8296732 (2021 national rates).
The claim format follows the filer. A hospital-based program bills the CMS-1450 with type of bill 013x, a critical access hospital with 085x, and a freestanding program with 087x. A professional claim uses the CMS-1500 and place of service 58.
The medication codes, and the setting that changes which ones work
The medication does not travel with the code. Inside a program the drug sits in the weekly bundle, so nothing else is billed for it. In an office, treatment is billed as a monthly bundle of management, coordination, therapy and counseling, and the medication is covered separately, often through the patient’s Part D plan.
The office-based codes are G2086 for the first calendar month at 70 minutes or more, G2087 for a later month at 60 minutes or more, and G2088 for each additional 30 minutes beyond 120. The settings do not share codes. CMS states that clinicians cannot use the program codes to bill for office-based treatment.
Telehealth does not change the setting marker. The Consolidated Appropriations Act, 2021 permanently removed the geographic and originating-site restrictions on behavioral health telehealth, so a patient’s home can be the originating site and audio-only technology is permitted. CMS states that the in-person visit condition in section 1834(m) applies after December 31, 2027.
Testing codes, and the frequency limits welded to them
Drug testing here splits into two families. Presumptive testing reports the presence or absence of a drug or drug class, billed with 80305, 80306 or 80307. Definitive testing identifies specific drugs and metabolites with a concentration, billed with G0480 through G0483, tiered by how many drug classes the profile reports.
Drug classes reported by each definitive testing code
Source: CMS HCPCS Level II descriptors for G0480 to G0483, published in CMS clinical laboratory fee schedule determinations.
The frequency limits attach to the code family, not to the laboratory. The controlled substance testing policy pays one presumptive result per patient per date of service regardless of how many providers bill, and holds a definitive code to the same per-day limit.
That policy then sets frequency by stage of abstinence. From 0 to 90 consecutive days, presumptive testing is expected at 1 to 3 a week, and more than 3 in one week is not covered. Past 90 days it drops to 1 to 3 a month. Definitive testing runs at not more than 1 profile a week in the first 30 days, then 1 to 3 a month.
A test beyond the documented ceiling is denied on reasonable and necessary grounds, not because the code is wrong. That distinction decides the appeal. Send the record showing the abstinence interval, the testing history and the clinician’s stated reason for the order.
Authorization by level, and the criteria a plan applies
Authorization tracks the level, and it differs between payers. In one commercial plan’s grid, partial hospitalization at ASAM level 2.5 needs prior authorization, while the level 2.1 intensive outpatient program needs notification at admission and authorization only after 15 sessions. Another large commercial payer requires authorization for every outpatient partial hospitalization and intensive outpatient service its policy lists.
Read the payer’s grid rather than a general rule. The same revenue code can sit under notification at one plan and authorization at another, and the session count that flips one into the other is plan specific. That count belongs on the authorization log beside the date.
The clinical test behind the request is usually a level-of-care criteria set. The one most often named here is The ASAM Criteria, published and owned by the American Society of Addiction Medicine. Plans license other criteria products too: one commercial behavioral health policy states that its utilization review clinicians apply InterQual criteria. A medical necessity appeal has to answer the version the plan applied.
The reviewer reads the authorization on file, the level the documentation supports, and the code on the claim. When those three disagree, the denial turns on whether the record described the level the plan was paying for, not on whether the treatment was appropriate.
The confidentiality rule that is unique to this service line
One federal rule reaches this service line and almost nothing else in a billing office. Records of a patient’s substance use disorder treatment are governed by 42 CFR Part 2, which sits on top of HIPAA. A Part 2 program is a federally assisted program providing substance use disorder diagnosis, treatment or referral. The regulation defines records to include information created, received or acquired by the program, and billing information is named in that definition.
The difference from HIPAA is in the default. HIPAA lets a covered entity use and disclose protected health information for treatment, payment and health care operations. Part 2 states that records subject to it may be used or disclosed only as permitted by Part 2. The restriction applies whether or not the program believes the requester already has the information, has other means of obtaining it, has a subpoena, or asserts another justification.
Two provisions matter to billing staff. A single consent can cover all future uses and disclosures for treatment, payment and health care operations, and a covered entity that receives records under it may redisclose them as HIPAA allows, other than in legal proceedings against the patient. Part 2 has no catch-all provision permitting a disclosure because another law requires it. The version to work from is the final rule effective April 16, 2024, with compliance required by February 16, 2026.
Whether a particular request can be answered is a legal question for the privacy officer or counsel. What a billing team needs is narrower: recognize when the record in front of you is a Part 2 record, do not act outside the consent on file, and route anything unusual to the privacy officer.
The denials that recur in this service line
Five denials repeat here, and each has a different owner. Naming the owner is what stops the same denial arriving again next month.
| Denial | What the remittance says | CARC | Owner |
|---|---|---|---|
| Authorization obtained for the wrong level | Precertification or authorization absent | 197 | Intake and authorization desk |
| Level change without a new request | Authorization exceeded, or a level of care change adjustment | 198 or 186 | Clinical team and authorization desk |
| Testing frequency exceeded | Information does not support this frequency of services | 151 | Coding and documentation |
| Setting the plan does not buy | Inappropriate or invalid place of service | 58 | Coding and contracting |
| Documentation that does not establish the level | Not deemed medically necessary by the payer | 50 | Clinical documentation |
CARC 15 is the code most denial reports still show for a missing authorization. X12 stopped it on May 1, 2018, and modified CARC 197 on the same date. A report carrying CARC 15 volume in 2026 is running on a retired list. Read 197 as absent, 198 as exceeded, and 284 as a number that is valid but does not apply to the billed service.
The level-change denial is the one to design around. When the clinician moves a patient up or down, the payer sees a service outside the authorized span of days or sessions. The request for the new level has to go out on or before the day of the change, with the record that explains the move. The setting denial is usually a contracting problem wearing a coding disguise: a plan may buy residential care at a licensed facility and not at a sober living home.
- 01
Before the first visit at a new level
Read the payer’s authorization grid for that level and record whether it triggers notification, authorization, or neither. Note the session count that changes the trigger.
- 02
On the day the level changes
File the request for the new level the same day. A level change mid-episode without a new authorization is the denial this step exists to prevent.
- 03
When the testing order is written
Check the order against the documented abstinence interval and the frequency ceiling before the specimen is drawn. A frequency limit cannot be corrected after the fact.
- 04
Before the claim leaves
Confirm the code family matches the setting the plan buys, and that place of service and revenue code agree with each other and with the authorization on file.
- 05
At the appeal
Send the medical necessity record for a coverage denial and the authorization trail for an authorization denial. They need different paper.
Two neighbors share the same payer logic: behavioral health carve-outs, where a separate vendor owns the authorization, and behavioral health diagnosis coding, where the diagnosis has to support the level the plan paid for.
Questions practices ask us about this
What makes substance use disorder billing different from other behavioral health?
The benefit is organized around a level of care rather than a diagnosis, so the level drives the code and the authorization. Medicare pays for medication through a weekly bundle at an opioid treatment program instead of through office codes. And the treatment record itself is governed by 42 CFR Part 2, a federal rule that reaches this service line and almost nothing else.
How does Medicare pay for medication in an opioid treatment program?
With a bundled payment for a weekly episode of care. The drug cost sits inside the bundle billed with a G-code such as G2067 for methadone or G2068 for oral buprenorphine, and the bundle also covers dispensing, counseling, individual and group therapy, and toxicology testing if performed. Only a Medicare-enrolled program can bill those codes, and there is no patient copayment.
Can a prescriber bill the opioid treatment program codes in an office?
No. CMS states that clinicians cannot use the opioid treatment program codes to bill for office-based treatment. Office-based care uses G2086 in the first calendar month, G2087 in a later month, and G2088 for each additional 30 minutes beyond 120 minutes. The prescribed medication is billed separately, and a patient with Part D coverage may have it covered by that plan.
How often will Medicare pay for drug testing in substance use disorder treatment?
One presumptive result is paid per patient per date of service regardless of how many providers bill, and definitive testing carries the same per-day limit. Frequency then follows the abstinence stage. From 0 to 90 consecutive days, presumptive testing is expected at 1 to 3 a week, and more than 3 in a week is not covered. Past 90 days it drops to 1 to 3 a month.
What does 42 CFR Part 2 mean for a billing department?
Part 2 covers records of substance use disorder diagnosis, treatment and referral, and it defines records to include billing information. It permits use and disclosure only as the regulation allows, whether or not the requester already has the information or holds a subpoena. It has no catch-all provision permitting a disclosure because another law requires it, so anything outside the consent on file goes to the privacy officer.
Who owns the level of care criteria a plan applies?
The organization that publishes the criteria product. The set most often named in these authorizations is The ASAM Criteria, published and owned by the American Society of Addiction Medicine, which licenses its use. Plans license other products as well, and one large commercial payer’s behavioral health policy states that its utilization review clinicians apply InterQual criteria.
Carrying a substance use disorder book?
We run authorization, coding and denial work for behavioral health and addiction medicine practices and keep the prior authorization log beside the claim. A revenue cycle health check shows where denials start.
Book a free billing review- CMS, Opioid Treatment Programs (OTPs) Billing & Payment. cms.gov/medicare/payment/opioid-treatment-program/billing-payment
- CMS, Office-Based Substance Use Disorder (SUD) Treatment Billing. cms.gov/medicare/payment/opioid-treatment-programs-otp/billing-payment/office-based-opioid-use-disorder-oud-treatment-billing
- CMS, Opioid Treatment Programs (OTPs) Medicare Billing and Payment, MLN8296732. cms.gov/files/document/otp-billing-and-payment-fact-sheet.pdf
- eCFR, 42 CFR Part 2, Confidentiality of Substance Use Disorder Patient Records. ecfr.gov/current/title-42/chapter-I/subchapter-A/part-2
- HHS, fact sheet on the 42 CFR Part 2 final rule. hhs.gov/hipaa/for-professionals/regulatory-initiatives/fact-sheet-42-cfr-part-2-final-rule/index.html
- CMS Medicare Coverage Database, LCD L36393, Controlled Substance Monitoring and Drugs of Abuse Testing. cms.gov/medicare-coverage-database/view/lcd.aspx?lcdid=36393
- UnitedHealthcare, Rocky Mountain Health Plans behavioral health prior authorization grid (April 2026). uhcprovider.com/content/dam/provider/docs/public/commplan/co/prior-auth/CO-RMHP-RAE-Prime-BH-Prior-Auth-04-1-2026.pdf
- X12, Claim Adjustment Reason Codes (current list). x12.org/codes/claim-adjustment-reason-codes
- Blue Cross Blue Shield of Massachusetts, medical policy 194, Behavioral Health Continuum of Care. bluecrossma.org/medical-policies/sites/g/files/csphws2091/files/acquiadam-assets/194%20Behavioral%20Health%20Continuum%20of%20Care.pdf
- American Society of Addiction Medicine, The ASAM Criteria, Fourth Edition. asam.org/asam-criteria/asam-criteria-4th-edition
- CMS, Telehealth FAQ on behavioral health telehealth and section 1834(m). cms.gov/files/document/telehealth-faq-updated-02-26-2026.pdf


