

Most behavioral health coding failures sit on the diagnosis, not on the service. Chapter 5 of ICD-10-CM holds the mental, behavioral and neurodevelopmental codes, the F10-F19 block inside it holds substance use, and the fourth, fifth and sixth characters carry the specificity, remission and severity a payer queries. One missing character is enough to lose a claim.
The chapter a behavioral health coder works inside
Chapter 5 of ICD-10-CM is where the mental health codes live. The FY 2027 ICD-10-CM Official Guidelines title it “Mental, Behavioral and Neurodevelopmental disorders (F01 – F99)”. The CDC code file for the same year lists 872 billable codes in that range, and the block headed “Mental and behavioral disorders due to psychoactive substance use” holds 458 of them.
A pass through the alphabetic index lands on a category, not a usable code. F10 is Alcohol related disorders. F10.1 is Alcohol abuse, F10.2 is Alcohol dependence, and F10.9 is Alcohol use, unspecified. The same split repeats for every substance family, because the pattern of use is a character position, not a sentence.
Substance codes also sit outside Chapter 5. Chapter 21 carries Z72.0 Tobacco use, Z87.891 Personal history of nicotine dependence, Z86.59 Personal history of other mental and behavioral disorders, and Z79.891 Long term (current) use of opiate analgesic. Long term use, dependence and history are three different statements.
| Family in the CDC file | Subcategories under it | Character that carries the pattern | Worked example |
|---|---|---|---|
| F10 Alcohol related disorders | F10.1 abuse, F10.2 dependence, F10.9 use, unspecified | Fifth | F10.21 Alcohol dependence, in remission |
| F11 Opioid related disorders | F11.1 abuse, F11.2 dependence, F11.9 use, unspecified | Fifth | F11.13 Opioid abuse with withdrawal |
| F17 Nicotine dependence | F17.2- only; no nicotine use, unspecified code | Fifth names the product | F17.210 Nicotine dependence, cigarettes, uncomplicated |
Billable codes per substance family
Source: CDC and NCHS, ICD-10-CM FY 2027 code descriptions file.
The guideline lists the unspecified use codes as F10.9- through F16.9-, plus F18.9- and F19.9-, and leaves F17 out. The FY 2027 file agrees: no nicotine code exists for use, unspecified.
Specificity is the part payers query
The guidelines are blunt about length. Diagnosis codes go out “at their highest number of characters available and to the highest level of specificity documented in the medical record”, and “a code is invalid if it has not been coded to the full number of characters required for that code”. A three-character code is correct only where the classification does not subdivide it.
Where the record stops short, the classification supplies a default. A condition documented without the extra detail takes the code listed next to the main term. A note that reads major depressive disorder, single episode and nothing more produces F32.9, Major depressive disorder, single episode, unspecified, rather than F32.1.
In the depressive families one position carries severity and remission. F32.0 is mild, F32.1 moderate, F32.2 severe without psychotic features, F32.3 severe with psychotic features, F32.4 in partial remission, F32.5 in full remission. The recurrent family adds a character for the remission state: F33.41 partial, F33.42 full.
Bipolar disorder splits the two ideas across two positions. One character names the current episode, the next names severity or remission. F31.11 is mild, F31.12 moderate and F31.13 severe, all for a current manic episode without psychotic features.
| Code | Official description (CDC, FY 2027) | What the note has to establish |
|---|---|---|
| F32.0 | Major depressive disorder, single episode, mild | A severity level the provider documented |
| F32.4 | Major depressive disorder, single episode, in partial remission | An episode resolving but not resolved |
| F33.42 | Major depressive disorder, recurrent, in full remission | A recurrent course and full remission |
| F31.31 | Bipolar disorder, current episode depressed, mild | Which episode is current, and its severity |
Severity is the level of the disorder the provider documented, not how sick the patient was on the day of the visit. Remission is the status of the disorder at the encounter, not how long the patient has been in treatment. Swap either one and the note stops supporting the code.
Remission codes and history codes are not interchangeable
For categories F10 through F19 the in-remission codes end in -.11, -.21 and -.91. The guideline is explicit about the evidence behind them: selecting one “requires the provider’s clinical judgment” and the codes “are assigned only on the basis of provider documentation”. An intake form does not substitute.
The same guideline decides which remission code a course gets. A mild substance use disorder in early or sustained remission is classified to the abuse in remission code. A moderate or severe disorder in early or sustained remission is classified to the dependence in remission code. A resolved severe disorder is F11.21, not F11.11.
History codes answer a different question. A personal history code describes a past condition that no longer exists and is not receiving treatment but may need continued monitoring, and the guideline allows history codes as secondary codes when the historical condition affects current care. Z87.891 is the history code for nicotine dependence. F17.201 is the in-remission code for the dependence itself.
| Code | Official description | What has to be true in the record |
|---|---|---|
| F10.21 | Alcohol dependence, in remission | A documented dependence and a documented remission |
| Z87.891 | Personal history of nicotine dependence | The dependence has resolved and is no longer treated |
| Z86.59 | Personal history of other mental and behavioral disorders | A past disorder that still affects care |
| Z79.891 | Long term (current) use of opiate analgesic | Ongoing use, which is not dependence and not history |
F10.20, Alcohol dependence, uncomplicated, is right while dependence is active and treated. Months later, on a note that describes sustained remission, the same code is a mismatch. The in-remission code is not a softer version of the active code. It is a different statement about the patient.
The documented substance changes the code
When the note describes use, abuse and dependence of the same substance, one code goes out, and the guideline sets the order. Use with abuse takes the abuse code, abuse with dependence takes dependence, and use with dependence takes dependence. All three documented: assign dependence.
The unspecified use codes are narrower than they look. The guideline permits F10.9- through F16.9-, plus F18.9- and F19.9-, only when the substance use is associated with a substance related disorder or a medical condition, and the provider documented that relationship. A positive screen on its own does not meet the test.
Character positions differ by substance. Withdrawal in alcohol dependence needs the full run: F10.230, Alcohol dependence with withdrawal, uncomplicated. The same state in an opioid record is a five-character code, F11.13, Opioid abuse with withdrawal. In the nicotine family the character after F17.2 names the product: F17.210 cigarettes, F17.220 chewing tobacco, F17.290 another tobacco product.
A medical condition caused by a substance is not a substance-induced disorder. The guideline directs the coder to assign the medical condition and the F10-F19 code rather than the “with other …-induced disorder” code, using alcoholic pancreatitis as its own example: K85.2 plus F10.20, not F10.288.
Blood alcohol level is a special case. A code from category Y90 may be assigned when the level is documented and the provider has documented a condition classifiable to F10. The level itself is one of the few items a clinician other than the patient’s provider may document. The F10 condition still has to be the provider’s.
- Read the fifth character before the sixth. It separates abuse, dependence and use nobody pinned down.
- Code the substance the note names, not the one a screen flagged.
- When the note documents a medical consequence, code both conditions.
The documentation the diagnosis has to sit on
The guideline on code assignment and clinical criteria settles the argument. Code assignment “is based on the provider’s diagnostic statement that the condition exists”, and that statement is sufficient. It is not based on the clinical criteria the provider used to reach the diagnosis. Where documents conflict, the answer is a query.
I.B.14 says whose words count. Code assignment rests on the documentation of the patient’s provider, the practitioner legally accountable for establishing the diagnosis. Other clinicians may document a short list of specific items, blood alcohol level among them, but the associated diagnosis has to be the provider’s.
The CMS Medicare Learning Network booklet on mental health coverage, updated in March 2026, states the claim-level test. Services must be reasonable and necessary for the diagnosis and treatment of the patient’s condition, must meet national and local coverage medical necessity criteria, and the practice has to state the specific sign, symptom or complaint for every service billed.
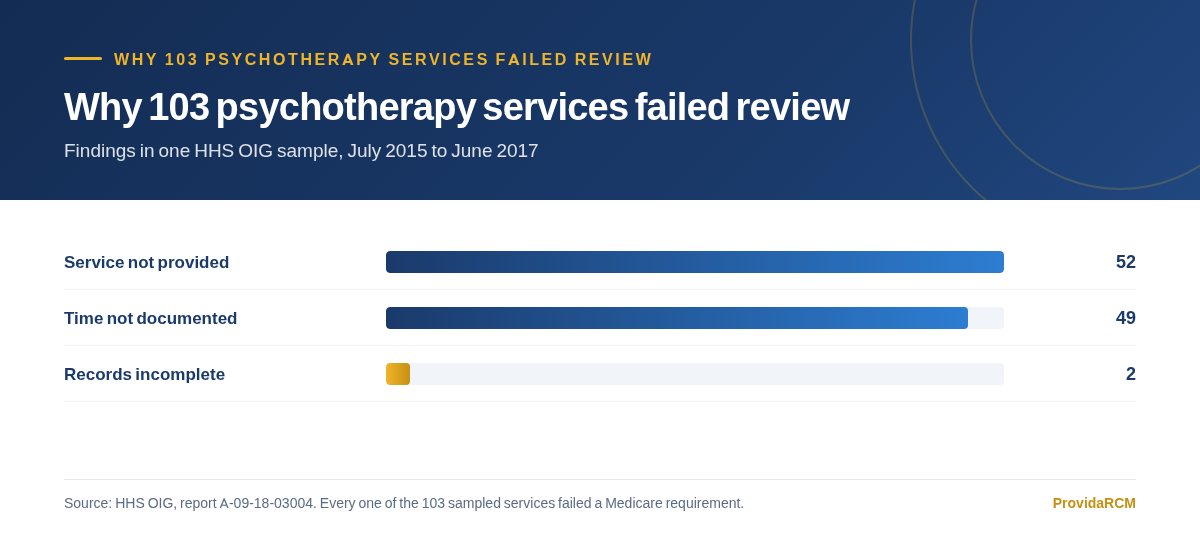
The Inspector General’s auditors preview what a reviewer asks for. In the Oceanside Medical Group review, 52 of the 103 sampled services had no evidence the service was provided, 49 had no documentation of psychotherapy time and 2 lacked supporting documentation. The audit estimated $2.6 million in unallowable payments.
- The diagnosis in the provider’s words, with the severity or remission level the code carries
- The substance named, when a code from F10 through F19 is on the claim
- The time the service took, when the service code is time based
- A treatment plan that is signed, and a reason for this encounter
Why behavioral health coding fails on the pairing
A claim is a pairing: one diagnosis, one service, one date. The X12 claim adjustment reason code list still carries CARC 11, active since 1995 and last modified in July 2017, worded “The diagnosis is inconsistent with the procedure”. Most diagnosis defects reach the payer as that or as a request for records.
| Error | What the claim shows | What follows |
|---|---|---|
| An unspecified code where a specific one exists | F32.9 on a note that documents moderate severity | A records request or a denial; the code should have been F32.1 |
| A severity character that contradicts the note | F31.13 against a note describing mild symptoms | A code and documentation mismatch, and a provider query |
| No substance use code when the note documents use | No F10-F19 code on a claim whose note describes daily use | The diagnosis on the record is not on the claim |
| A diagnosis carried forward from a previous encounter | Last visit’s F33.1 on today’s claim | A claim describing an encounter that did not happen |
Every one of those has the same root. The coder worked from a template, the previous claim or the appointment type rather than from what the provider wrote for this encounter. Where the record conflicts with itself, the guideline’s answer is a query, and a query costs less than a denial.
- 01
Read the assessment before the codes
The provider’s diagnostic statement is the source. Everything else on the claim follows from it.
- 02
Check the length of every code
If a code stops short of the characters the classification allows, look for the missing detail in the note before the claim goes out.
- 03
Query rather than guess
A conflicting note is a question for the provider. Coded assumptions are what auditors find.
What the diagnosis decides after the service is delivered
None of this is a clinical argument. The diagnosis code is the field a payer uses for authorisation, coverage and audit selection. Authorisations are granted against a diagnosis and a number of units, so a diagnosis change mid-authorisation changes what the payer agreed to pay for. Our work on ABA units and authorizations and telehealth billing rules starts there.
Coverage is decided against written criteria. The Medicare Learning Network states that services must meet national and local coverage determination medical necessity criteria, and those criteria are written around conditions. A claim cannot be matched to a policy it does not name, which is why medical necessity denial appeals have to answer the payer’s criteria in order.
Audit selection follows the claim pattern. The Inspector General did not pick the Oceanside review at random: claim analysis showed providers billing an average of 33 individual services per day, and two billing on all but five days of the audit period.
Estimated unallowable Medicare payments, two psychotherapy audits
Source: HHS OIG reports A-09-18-03004 (August 2019) and A-02-21-01006 (March 2022).
Specificity lowers the chance that a claim is queried. It does not guarantee that a payer covers the service, because coverage runs through the payer’s own medical policy. The coding question and the coverage question are separate.
The practices that stop seeing these denials code to the last character the classification provides, send the substance and remission detail the note supports, and query the clinician before the claim leaves. That is what behavioral health billing and medical coding look like on the diagnosis side, and it is how we handle payer carve-outs and the October ICD-10-CM updates each year.
Questions practices ask us about this
What chapter of ICD-10-CM holds behavioral health diagnoses?
Chapter 5 runs from F01 to F99 and is titled Mental, Behavioral and Neurodevelopmental disorders. Inside it sits the block for mental and behavioral disorders due to psychoactive substance use, F10 through F19. Substance related codes also appear outside the chapter, in the Chapter 21 Z codes for history, tobacco use and long term drug use.
What is the difference between F10.11 and F10.21?
F10.11 is Alcohol abuse, in remission, and F10.21 is Alcohol dependence, in remission. The guideline routes a mild substance use disorder in early or sustained remission to the abuse code and a moderate or severe disorder to the dependence code, so the choice follows the severity of the disorder, not the time since the last drink.
When should a practice use a history code instead of an in-remission code?
A personal history code describes a condition that no longer exists and is not receiving treatment but may still need monitoring. Z87.891 reports a personal history of nicotine dependence, while F17.201 reports a nicotine dependence in remission. A condition still under treatment takes the in-remission code, not the history code.
How do we code a substance when the note documents both use and dependence?
Assign one code and let the guideline’s order decide. Use with abuse gives the abuse code, abuse with dependence gives dependence, and use with dependence gives dependence. When all three are documented, the dependence code is the only one that belongs on the claim.
What does CARC 11 mean on a behavioral health claim?
CARC 11 is the payer saying the diagnosis is inconsistent with the procedure. X12 lists it as active since 1995 and last modified in July 2017. On a behavioral health claim it usually means the diagnosis does not support the service billed, so the work goes back to coding, and sometimes to the clinician.
Why does a severity character cause a denial?
Because the code and the note have to agree. A severe code against a note describing mild symptoms, or the reverse, gives the payer a defensible reason to request records. The guideline requires codes at the highest level of specificity the record supports, so the code has to match what the provider documented.
Can we carry a diagnosis forward from the previous visit?
Only if the provider documents that condition for the current encounter. Code assignment is based on the provider’s diagnostic statement that the condition exists, and a conflict in the record calls for a query. A diagnosis copied from the last claim describes an earlier encounter, and the note will not support it.
A coding review before the payer runs one
We code behavioral health and ABA claims against the same conventions a payer’s reviewer applies: specificity checks before submission, queries back to the clinician, and appeal support for denials. Start with a revenue cycle health check.
Book a free coding review- ICD-10-CM Official Guidelines for Coding and Reporting, FY 2027 (CMS and NCHS). cms.gov/files/document/fy-2027-icd-10-cm-coding-guidelines.pdf
- CDC and NCHS, ICD-10-CM FY 2027 code descriptions and order files. ftp.cdc.gov/pub/Health_Statistics/NCHS/Publications/ICD10CM/2027
- CMS, ICD-10-CM tabular list and index files. cms.gov/medicare/coding-billing/icd-10-codes
- CMS MLN, Medicare and Mental Health Coverage (MLN1986542, March 2026). cms.gov/files/document/medicare-mental-health.pdf
- HHS OIG, Oceanside Medical Group psychotherapy services (A-09-18-03004). oig.hhs.gov/oas/reports/region9/91803004.asp
- HHS OIG, New York City psychotherapy provider (A-02-21-01006). oig.hhs.gov/oas/reports/region2/22101006.asp
- X12, Claim Adjustment Reason Codes, current list. x12.org/codes/claim-adjustment-reason-codes


