

MIPS 2026 comes down to three volume tests a practice has to exceed, four category weights, and one submission window that closes on March 31, 2027. Here is what the CY 2026 final rule requires, who is exempt, and the calendar that keeps reporting from becoming a spring emergency.
MIPS 2026 eligibility: three volume tests decide it
The 2026 performance period opened on January 1, 2026, and CMS finalized the rules that govern it in the CY 2026 Physician Fee Schedule final rule, published on November 5, 2025. Eligibility kept the same three-test structure, which is why practices get this wrong: they remember a threshold from a prior year and assume it still applies.
To be required to report for 2026, an individual clinician or a group has to exceed all three low-volume threshold criteria, measured across both 12-month segments of the MIPS determination period. Two out of three is not enough, and that mistake is common.
| Test for 2026 | Threshold | What CMS actually counts |
|---|---|---|
| Allowed charges | More than $90,000 | Medicare Part B allowed charges for covered professional services under the Physician Fee Schedule |
| Medicare patients | More than 200 | Distinct Medicare Part B beneficiaries who received your services |
| Covered services | More than 200 | Covered professional services furnished to those Medicare Part B patients |
The determination period runs in two 12-month segments that close before the year being measured, so eligibility for 2026 was set by claims billed in 2024 and 2025. A group that hired three clinicians this year is scored on volume those clinicians have not generated yet. CMS publishes the answer per TIN and NPI on the participation status tool and finalizes 2026 eligibility in December 2026.
Two answers can take a practice out of MIPS. Qualifying APM Participants in an Advanced APM are excluded and receive the 5% incentive instead, and Partial Qualifying APM Participants choose whether to report. CMS lowered both sets of thresholds for the 2026 performance year under the Consolidated Appropriations Act of 2026, so a group that sat close to the line last year may have crossed it.
Advanced APM thresholds for the 2026 performance period
Source: CMS Quality Payment Program, 2026 MIPS Eligibility Decision Tree.
Fall above one or two of the three volume tests and the decision belongs to you. CMS calls these clinicians opt-in eligible: you can elect to participate and be scored against the same threshold as everyone else, or voluntarily report and keep the feedback without joining. Fall below all three and you are outside MIPS for 2026. The medical billing glossary is useful here, because CMS treats opt-in, voluntary reporting and exclusion as three different statuses.
What each MIPS 2026 category is worth
Four performance categories feed the final score for the 2026 performance period: quality at 30%, cost at 30%, promoting interoperability at 25%, and improvement activities at 15%. Those weights have been stable since 2022. Cost is calculated for you from administrative claims, so there is nothing to submit, yet that category decides nearly a third of the score.
| Category | 2026 weight | What the practice submits | How it is scored |
|---|---|---|---|
| Quality | 30% | Six or more measures from the 2026 quality inventory, direct or through a registry | 1 to 10 points per measure against a historical benchmark |
| Cost | 30% | Nothing. CMS calculates every cost measure from administrative claims | Measures scored against national performance |
| Promoting Interoperability | 25% | Required measures plus four attestations, using certified EHR technology | A single No attestation can zero the category |
| Improvement Activities | 15% | Attestations for activities that each ran 90 continuous days | 40 points maximum, weighted by activity |
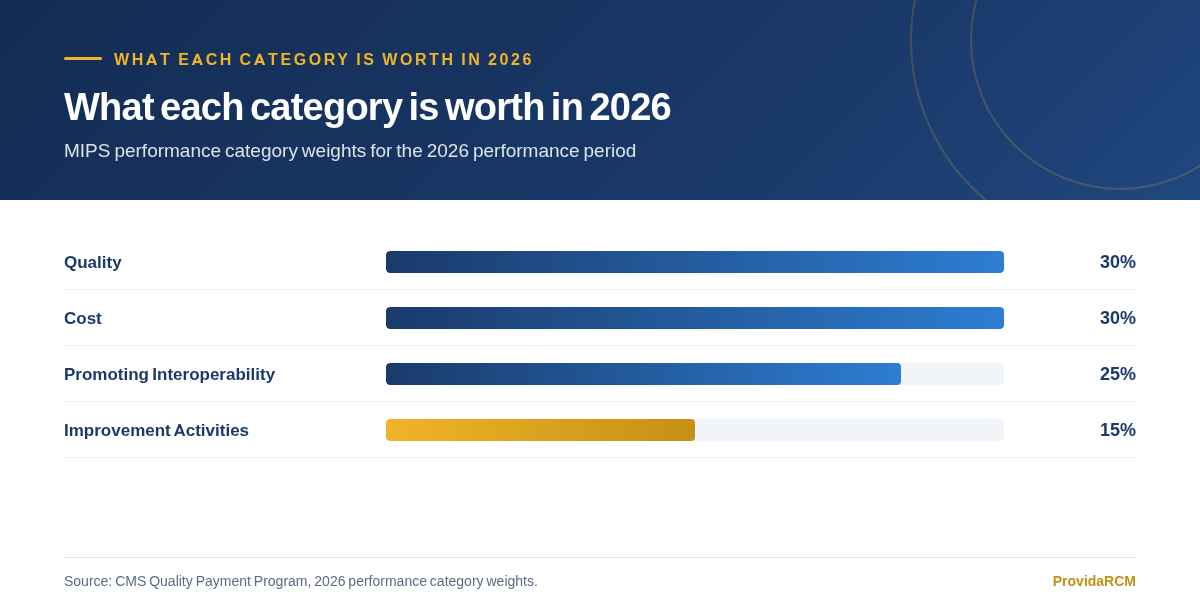
Each category score is a percentage of the points available in it, multiplied by its weight and added together. A practice that finishes every improvement activity perfectly and lets quality slide still loses, because 15% cannot cover a 30% gap. The lightest category is the wrong place to spend the year.
How the quality category actually works in 2026
Quality is the category a practice can still influence after December, because you choose the measures and the data has to come from the whole year. Each measure is scored from 1 to 10 points against a benchmark built from historical national performance. Traditional MIPS requires at least six measures, including at least one outcome or high priority measure.
The 2026 inventory holds 190 quality measures plus 198 Qualified Clinical Data Registry measures. CMS added five measures, removed ten, and made substantive changes to thirty of those that remain. Three of the changed measures lost their historical benchmark, so a 2024 measure list that was never reviewed is a real risk.
| Rule | 2026 requirement | Where it bites |
|---|---|---|
| Performance period | Twelve months, January 1 to December 31, 2026 | A late start cannot be repaired in January 2027 |
| Measure selection | At least six measures, including one outcome or high priority measure | Specialty sets with fewer than six measures allow fewer |
| Data completeness | At least 75% of each measure’s eligible population | Reporting only favorable cases fails the threshold |
| Case minimum | Each measure carries its own minimum number of cases | Below the minimum a measure scores zero, or three points for a small practice |
The data completeness bar is 75% for the 2026 performance period, and that figure is written into regulation for the 2026 through 2030 MIPS payment years under 42 CFR 414.1340. It is not a number that moves next spring. You must identify the full eligible population for the twelve-month period and report data or a denominator exception for three quarters of it.
Small practices keep their safety net. A measure that is reported but has no benchmark, or that falls below the case minimum, scores zero points for most clinicians and three points for a small practice. Those three points are often the difference between a penalty year and a neutral one, which is an argument for selecting measures with medical coding services rather than by habit.
MIPS Value Pathways in 2026: an option, not a requirement
An MVP is a narrower, specialty-shaped version of MIPS. You register for one pathway, then report four quality measures, one improvement activity from that pathway, and the same promoting interoperability measures everyone else reports. CMS calculates the two population health measures from claims and assigns whichever scores higher.
Twenty-seven MVPs are available for the 2026 performance period. CMS finalized six new pathways covering diagnostic radiology, interventional radiology, neuropsychology, pathology, podiatry and vascular surgery, and modified the twenty-one already in place. Each pathway stratifies its measures by clinical condition or episode of care, which makes the relevant ones easier to find.
An MVP suits a practice that can name its clinical focus and wants a shorter measure list. It does not suit a practice with a scattered payer mix and no dominant condition, because the four measures have to be meaningful for the clinicians reporting them. Registration is a commitment made in advance, and the window runs from April 1 to November 30, 2026.
Beginning with the 2026 performance period, a multispecialty group that wants to report an MVP has to register and participate at the subgroup level. Multispecialty small practices may still report an MVP as a group without forming subgroups. A group that registers the wrong way cannot fix the structure in March.
Traditional MIPS remains available for 2026, and nothing in the CY 2026 final rule forces a practice into a pathway. If no MVP carries four measures your clinicians report, six traditional measures with clean data completeness is the better trade.
Promoting Interoperability and Improvement Activities in 2026
Promoting Interoperability carries 25% of the final score and is graded against certified EHR technology. For 2026 the category runs through four objectives and six to seven required measures, plus attestations that can zero it. A No on the Security Risk Analysis measure or the High Priority Practices SAFER Guide measure scores zero points for the category, not for that measure alone.
Two measures changed this year. The Security Risk Analysis attestation now has a second component covering security risk management, on top of the existing requirement to attest that an analysis was conducted or reviewed under the HIPAA Security Rule. The SAFER Guide measure now requires the 2025 High Priority Practices Guide. CMS also adopted a measure suppression policy that takes effect with this performance period.
Some practices do not submit this category at all. Clinicians and groups that qualify for reweighting have the 25% redistributed to other categories and are scored on those instead. A hardship exception application, open from spring 2026 through December 31, 2026, is the route in for everyone else, and an approved exception can also cancel an automatic reweighting.
Improvement activities are the cheapest category to finish and the easiest to forget. You attest to completing them, each one has to run for at least 90 continuous days inside the 2026 performance period, and the category tops out at 40 points. CMS weights activities as medium or high, and small, rural, non-patient-facing and HPSA practices collect those points faster than everyone else. The 2026 inventory also retired the Achieving Health Equity subcategory and added Advancing Health and Wellness.
The 2026 reporting calendar and the payment adjustment it earns
MIPS pays out two years after the performance period. The 2025 data submitted in early 2026 drives the 2027 payment adjustment. The data collected during the 2026 performance period drives the 2028 payment adjustment, applied to Medicare claims from January 1, 2028 through December 31, 2028.
| Date | What happens | Who has to act |
|---|---|---|
| January 1, 2026 | Performance period opens and quality data collection begins | Every practice that will report |
| April 1 to June 30, 2026 | Registration for the CAHPS for MIPS survey | Practices that want the patient experience measure |
| April 1 to November 30, 2026 | MVP registration window | Groups and subgroups reporting a pathway |
| Spring to December 31, 2026 | Exception applications for Extreme and Uncontrollable Circumstances and Promoting Interoperability hardship | Practices seeking reweighting or category relief |
| December 2026 | CMS finalizes 2026 MIPS eligibility | Everyone. Check the participation status tool |
| January 2 to March 31, 2027 | Data submission window for the 2026 performance period | The practice, a registry, a QCDR or a vendor |
| January 1, 2028 | The 2028 payment adjustment takes effect | Nobody. It is applied to Medicare claims automatically |
The submission window for the 2026 data runs from January 2, 2027 to March 31, 2027. Quality data, improvement activity attestations and the interoperability submission all have to be inside it. A registry that goes dark in December, or a quality report that stops at 74% completeness, cannot be repaired after the window closes.
The score a practice needs in 2026 is 75 points. CMS finalized the performance threshold at 75 through the 2028 performance period, so the target is not the moving number it once was. Scores at or above 75 earn a zero or positive adjustment, and scores below 75 earn a negative one.
What a 2026 final score does to 2028 payments
Source: 42 CFR 414.1405, MIPS payment adjustment factors. Illustrative scores before the budget neutrality scaling factor.
The mechanics of the negative side matter more than the positive side. Under 42 CFR 414.1405 the adjustment slides linearly from 0% at the threshold to negative 9% at a final score of zero, and any score of 18.75 points or less takes the entire 9% cut. Positive adjustments pass through a scaling factor of up to 3.0 to keep the program budget neutral; the negative side is never scaled.
The gap between a 20 point score and a 60 point score is worth a few percentage points of Medicare revenue. The gap between 74 and 76 points decides the sign in front of it.
Running MIPS as a year-long habit, not a February scramble
Three habits carry the program. Collect quality data across all twelve months, because the 75% data completeness test cannot be backfilled. Run improvement activities on fixed 90-day blocks with a named owner and a date, so the attestation survives an audit. Check eligibility each December, when CMS finalizes it, so the first quarter is not spent discovering the practice is scored on volume it no longer has.
Assign one person to the calendar, because in most independent practices the failure is not a coding failure or a technology failure; it is that nobody owns the months between January and March. The 2026 Medicare Physician Fee Schedule changes set the payment backdrop, and the credentialing timeline still matters, since a clinician enrolled mid-year changes both measure denominators and reported volume.
The last two weeks of the window are where a reporting partner earns its keep: reconciling the registry file, confirming every attestation, and submitting before March 31, 2027. Our medical billing services and accounts receivable management teams carry that work as part of the revenue cycle, and they already hold the claims data behind the quality measures.
Questions practices ask us about this
What is the low-volume threshold for MIPS in 2026?
To be required to report for the 2026 performance period, a clinician or group has to exceed all three tests: more than $90,000 in Medicare Part B allowed charges for covered professional services, more than 200 Medicare Part B patients, and more than 200 covered professional services. All three are measured across both 12-month segments of the MIPS determination period, and all three have to be exceeded.
What are the MIPS performance category weights for 2026?
For the 2026 performance period the weights are quality 30%, cost 30%, promoting interoperability 25%, and improvement activities 15%. Cost is calculated by CMS from administrative claims, so there is nothing to submit for that category. The weights have been unchanged since 2022, and the CY 2026 Physician Fee Schedule final rule carried them forward.
How many quality measures do I have to report for the 2026 performance period?
Traditional MIPS requires at least six quality measures, including at least one outcome or high priority measure. MVP participants report at least four measures drawn from their selected pathway. Each measure then has to meet its own case minimum and cover at least 75% of its eligible population for the twelve-month period, or it scores zero points. Small practices receive three points for a reported measure that has no benchmark.
When does the 2026 MIPS data submission window open and close?
The submission window for the 2026 performance period runs from January 2, 2027 to March 31, 2027. Quality measures, improvement activity attestations and the interoperability submission all have to be in by then. CMS does not reopen the window, and a report that falls short of the data completeness threshold cannot be repaired afterwards.
What is the MIPS performance threshold for the 2026 performance period?
The threshold is 75 points, and CMS finalized it at 75 through the 2028 performance period. A final score of 75 or above earns a zero or positive payment adjustment. A score below 75 earns a negative adjustment on a linear slide, and any score of 18.75 points or lower takes the full 9% cut, the maximum for the 2028 payment year.
Which payment year does the 2026 performance period affect?
MIPS payment adjustments are applied two years after the performance period, so the 2026 data drives the 2028 payment year, running from January 1, 2028 through December 31, 2028. The 2027 payment adjustment comes from the 2025 performance period instead.
Want this fixed in your practice?
We run full-cycle billing, coding, credentialing and denial work for practices across the country. Send us a few months of claims and we will show you where the money is going.
Book a free billing review- CMS Quality Payment Program, 2026 MIPS Eligibility Decision Tree (low-volume threshold and Advanced APM thresholds). qpp.cms.gov/content-management/resources/document/7fe01266-10ff-4095-8bf7-d9537c97d7b8/download/file
- CMS Quality Payment Program, timeline and important deadlines for the 2026 performance year. qpp.cms.gov/resources/timeline
- Medicare and Medicaid Programs; CY 2026 Payment Policies under the Physician Fee Schedule (final rule, 90 FR 49266, November 5, 2025). federalregister.gov/documents/2025/11/05/2025-19787/medicare-and-medicaid-programs-cy-2026-payment-policies-under-the-physician-fee-schedule-and-other
- CMS Quality Payment Program, 2026 Final Rule Fact Sheet and Policy Comparison Table. qpp-cm-prod-content.s3.amazonaws.com/uploads/3506/2026%20Quality%20Payment%20Program%20Final%20Rule%20Fact%20Sheet%20and%20Policy%20Comparison%20Table.pdf
- 42 CFR 414.1405, MIPS payment adjustment factors, performance threshold and scaling factor. ecfr.gov/current/title-42/section-414.1405
- 42 CFR 414.1340, data completeness criteria for the quality performance category. ecfr.gov/current/title-42/section-414.1340
- CMS Quality Payment Program, 2026 Finalized MIPS Value Pathways. qpp-cm-prod-content.s3.amazonaws.com/uploads/3509/2026-Finalized-MVPs-Guide.pdf


