ICD-10 updates land on October 1 every year, the first day of the federal fiscal year, and the FY 2027 set is already live. The work that matters happens upstream: charge tickets, EHR templates, encoders, clearinghouse edits, payer crosswalks, and denial monitoring on the codes that changed status.
How ICD-10 updates are scheduled each year
ICD-10-CM and ICD-10-PCS change on October 1, the first day of the federal fiscal year. The set that governs a claim is fixed by the date of service for professional and outpatient claims and the date of discharge for inpatient claims, not by the day the claim is keyed. A visit on September 30, 2026 is coded from the FY 2026 set even if it is billed in November. There is no grace period and no overlap between code years.
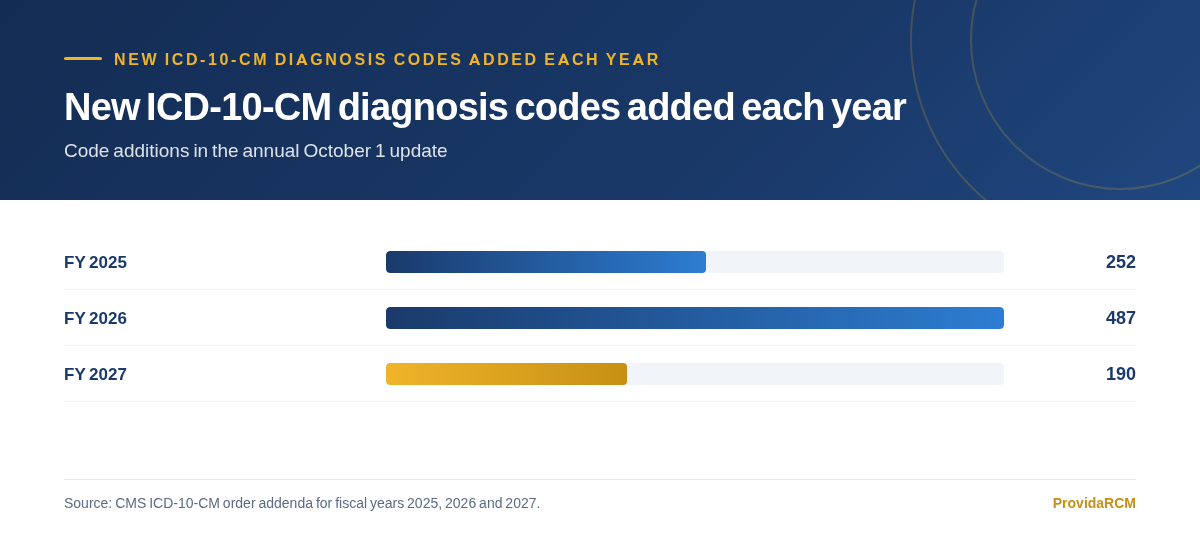
The FY 2027 ICD-10-CM set took effect October 1, 2026. Counting the rows in the CMS order addenda, it adds 190 billable diagnosis codes, deletes 30, and revises four titles, moving the code set from 74,719 codes to 74,879. The FY 2026 update was far larger at 487 additions, so the size of the annual change moves a lot from year to year.
What changed in the FY 2027 ICD-10-CM set
Source: CMS FY 2027 ICD-10-CM order addenda (icd10cm_order_addenda_2027).
| Milestone | When it happened | What it decides |
|---|---|---|
| Coordination and Maintenance Committee, spring meeting | March 17 to 18, 2026 | Diagnosis and procedure codes proposed for October 1, 2026 are presented and opened to comment |
| Public comment deadline | April 17, 2026 | Closes the record on the codes proposed for the October 1, 2026 update |
| Final files and addenda published | June 2026 | The code set is locked and every vendor has the final files |
| Effective date | October 1, 2026 | The FY 2027 set governs each claim by date of service or discharge |
| Next cycle already open | March 2026 onward | Codes proposed for October 1, 2027 are in the comment stage now |
The volume of the change matters less than the timing. Every step runs on a fixed date, and the files that carry the change publish about three months before the codes take effect. That gap is the whole preparation window, and a practice that starts when the claims deny has already spent it.
What the ICD-10 code freeze covers now
CMS ran a partial code freeze on ICD-10-CM and ICD-10-PCS from the 2011 code year until it ended on October 1, 2016, one year after ICD-10 went live. The CMS freeze notice says only codes for new technologies and new diseases were added during that window. That history is why the phrase still turns up in vendor material, and why it is still read as a present-tense rule.
The freeze is over, and ICD-10 receives full annual updates. What limits change today is the cycle itself. The final addenda publish in June, roughly three months before the October 1 effective date, and after that the year’s code set is fixed except for errata. The one channel that can still add codes between October updates is the April 1 new-technology path.
For a practice that reframes the question. It is not whether a code can still be added, because the October set is already final by the time the files appear. It is whether every system has loaded that final set before the effective date, and whether the team knows which codes changed status inside it.
Where the official files and addenda are published
Every count here comes from the files CMS and the CDC publish, not from a third-party code list. The CMS ICD-10 page carries the FY 2027 diagnosis and procedure files, and the CDC National Center for Health Statistics publishes the same diagnosis set on its own site. The Coordination and Maintenance Committee materials show what was proposed before it was final.
Two files settle any argument about what changed. The order addenda list every addition, deletion and revision as a single row, which is the only reliable way to count the change. The addendum PDFs carry the tabular, index and drug-table corrections behind those rows, and the conversion table maps a code across the code-year boundary.
| File | What it contains | Where it is published |
|---|---|---|
| Order addenda | Every code addition, deletion and revision as one row | CMS ICD-10 page |
| Addendum PDFs | Tabular, index and drug-table changes behind the code rows | CMS ICD-10 page |
| Code descriptions in tabular order | The full code list with long and short titles | CMS ICD-10 page and CDC NCHS |
| Conversion table | Maps codes across the code-year boundary | CMS ICD-10 page and CDC NCHS |
| Official coding guidelines | The reporting rules that travel with the code set | CMS ICD-10 page |
| MLN fact sheet on code sets | Plain-language background on health care code sets | CMS Medicare Learning Network |
Pull the order addenda into a spreadsheet on the day they publish. Filter to the codes your practice actually bills, and you have a working list of templates to fix and codes to watch, weeks before the payer edit changes.
The ICD-10-PCS update on the facility side
ICD-10-PCS codes describe inpatient procedures, and they run on a shorter clock than diagnosis codes. The FY 2027 PCS set applies to discharges from October 1, 2026 through March 31, 2027, then a mid-year update takes over for April 1 through September 30. A hospital grouper and its code editor both have to move on that schedule.
The FY 2027 PCS update adds 101 procedure codes, deletes 38 and revises three, bringing the code set to 79,256 codes. Many of the additions land in the New Technology section, which exists for procedures tied to devices and drugs that need a code before the next full cycle. The FY 2027 inpatient rule pairs those codes with a new MS-DRG grouper version and a matching code editor.
What changed in the FY 2027 ICD-10-PCS set
Source: CMS FY 2027 ICD-10-PCS order addenda (order_addenda_2027).
The April 1 path for new technology
New technology does not wait for October. CMS publishes a mid-year ICD-10-PCS update effective April 1 each year, and it is a real code set change rather than an errata pass. The April 1, 2026 update added 80 procedure codes, deleted two and revised one, covering devices and therapies that cleared review after the prior October cycle closed.
Most of the April additions sit in Section X, the New Technology section of ICD-10-PCS. A facility that runs a single October cutover and forgets the spring update ends up with a grouper that cannot classify the new procedures. Build April 1 into the same calendar as October 1 so the grouper, editor and encoder all move twice a year.
Diagnosis codes change once a fiscal year for a practice. Procedure codes on the facility side change twice, on October 1 and again on April 1. The spring update is smaller, but it lands in the middle of the year with no October-style ramp, so it is the one teams forget.
The practice checklist before October
The coding change is the easy part. The work is every system downstream of the code that has to know the new set before the effective date. Miss one and the claims go out carrying a code the payer will not take, and the denial shows up weeks after the switch.
- Load the new code set into the encoder and the EHR pick list, then test lookups on the codes that changed
- Rebuild charge tickets and encounter forms for any code that was added, deleted or moved to non-billable
- Review the superbill for retired codes, because a deleted code on a paper form keeps getting billed until someone removes it
- Confirm clearinghouse and payer edits use the new set on day one, and ask each major payer for its crosswalk
- Update the payer crosswalks and medical-policy lists that map a code to coverage
- Give each system an owner and a test date, and log who signed off
| System | What changes | Owner | When |
|---|---|---|---|
| Encoder | New, deleted and revised codes loaded and tested | Coding lead | About 60 days out |
| EHR and templates | Pick lists, charge tickets and encounter forms rebuilt | Clinical informatics | 30 days out |
| Superbill | Retired and demoted codes removed | Billing manager | 30 days out |
| Clearinghouse | Claim edits and payer rules updated to the new set | Billing operations | Before October 1 |
| Payer crosswalks | Coverage and medical-policy mappings refreshed | Contracting and billing | Before October 1 |
| Grouper and code editor | Facility software moved to the matching version | HIM and IT | About 6 weeks out |
None of this needs new software. It needs a list, a date and a name next to each line. A practice that runs medical coding and billing through the same team usually finds the template and superbill problems during a single review, because the people building the charge tickets are the people who will see the denials.
Denial monitoring in the first weeks after the switch
Expect a spike on the codes that changed status. On the 835 remittance, a code the software has not loaded or the payer has not accepted typically returns as CARC 16, claim or service lacks information or has a submission or billing error. It is often paired with a remark code such as M76, missing, incomplete or invalid diagnosis. Both are current on the X12 code lists, and M76 has no stop date.
The highest-risk codes are the ones that were billable and are not anymore. When a parent code is demoted to a non-billable header, every template, favorite list and payer policy that still produces it generates a rejected line. I42.0, dilated cardiomyopathy, is the FY 2027 example: the old code became a header, and it now requires a child code for the specific type. Any workflow still dropping the parent code needs a rebuild, not a reminder.
Deleted and demoted codes do not announce themselves. A code that stopped being billable on October 1 can sit in a charge ticket or a favorite list for months, producing denials that look like payer behavior rather than a template problem. The order addenda name every one of them, including the demotions that hide behind an unchanged code number.
- 01
Pull the first two weeks of remittances by code
Group denials by the diagnosis or procedure code on the claim, not by payer. The pattern shows up faster at the code level.
- 02
Match denied codes against the change list
Line up the denied codes against the order addenda. If a denied code is one that was deleted or demoted, the claim is a symptom, not the disease.
- 03
Fix the source, not the claim
Correct the template, pick list or crosswalk that produced the code, then resubmit. Resubmitting without fixing the source just repeats the denial next month.
Run that review monthly for the first quarter after the switch, then fold it into routine denial management. The goal is simple: the October change should cost a few weeks of cleanup, not a permanently higher denial rate.
Questions practices ask us about this
When do the ICD-10 updates take effect?
ICD-10-CM and ICD-10-PCS both update on October 1, the first day of the federal fiscal year. The FY 2027 set took effect October 1, 2026 and runs through September 30, 2027 for diagnosis codes. The code that applies to a claim follows the date of service or the date of discharge, not the date the claim is submitted.
Is ICD-10 still under a code freeze?
No. CMS ran a partial code freeze from the 2011 code year until it ended October 1, 2016, one year after ICD-10 went live, and only new technology and new disease codes could be added during it. ICD-10 now receives full annual updates. Vendor material that still describes an active freeze is usually describing that historical window.
How many ICD-10-CM codes changed for FY 2027?
The FY 2027 ICD-10-CM set adds 190 billable diagnosis codes, deletes 30 and revises four titles, moving the set from 74,719 codes to 74,879. The count comes from the CMS order addenda, which list every addition, deletion and revision as a row. Third-party summaries sometimes report different totals because they count headers as well as codes.
Do ICD-10-PCS codes change on the same schedule as ICD-10-CM?
They share the October 1 start but not the whole year. The FY 2027 ICD-10-PCS set applies to inpatient discharges from October 1, 2026 through March 31, 2027. CMS publishes a separate mid-year procedure update effective April 1, so a facility runs two code cutovers in a fiscal year while a practice runs one.
Where do we download the official ICD-10 updates?
The CMS ICD-10 page carries the ICD-10-CM and ICD-10-PCS files, including the addenda, order addenda, conversion tables and coding guidelines. The CDC National Center for Health Statistics publishes the same diagnosis set. Read the order addenda first, because they list each change as a single row and settle any dispute about the totals.
What is the biggest denial risk after the October 1 switch?
Codes that were billable and are not anymore. When a parent code is demoted to a non-billable header, every template and favorite list that still produces it generates a rejected line, which typically returns as CARC 16 with a diagnosis remark such as M76. Dilated cardiomyopathy, code I42.0, is the FY 2027 example.
Want this fixed in your practice?
We run full-cycle billing, coding, credentialing and denial work for practices across the country. Send us a few months of claims and we will show you where the money is going.
Book a free billing review- CMS, ICD-10 code files and addenda (FY 2027). cms.gov/medicare/coding-billing/icd-10-codes
- CMS, Hospital Inpatient Prospective Payment Systems, FY 2027 final rule, 91 FR 49570 (Federal Register, August 4, 2026). federalregister.gov/documents/2026/08/04/2026-15833/medicare-program-hospital-inpatient-prospective-payment-systems-for-acute-care-hospitals-ipps-and
- CMS, ICD-10 Coordination and Maintenance Committee procedure code materials. cms.gov/medicare/coding-billing/icd-10-codes/icd-10-coordination-maintenance-committee-materials
- CMS, Partial Code Freeze for ICD-9-CM and ICD-10. cms.gov/medicare/coding/icd10/downloads/partial_code_freeze.pdf
- CDC National Center for Health Statistics, ICD-10-CM Coordination and Maintenance Committee meetings. cdc.gov/nchs/icd/icd-10-maintenance/meetings.html
- CMS Medicare Learning Network, Health Care Code Sets fact sheet. cms.gov/files/document/mln900943-health-care-code-sets.pdf
- X12, Remittance Advice Remark Codes (current list). x12.org/codes/remittance-advice-remark-codes