
The Medicare Physician Fee Schedule 2026 raised the headline conversion factor for most practices, to $33.4009, a 3.26 percent increase over 2025. Underneath that number sit two conversion factors, a 2.5 percent work RVU efficiency adjustment on thousands of non-time-based codes, and a practice expense shift that moves money between hospital and office settings.
Medicare Physician Fee Schedule 2026: how a payment is built
Every Medicare payment under the fee schedule is arithmetic, not negotiation. The formula is [(work RVU x work GPCI) + (practice expense RVU x PE GPCI) + (malpractice RVU x MP GPCI)] x conversion factor. The three RVUs measure relative resources. The geographic practice cost indices adjust for local wages, rent, and insurance costs. The conversion factor turns all of it into dollars. CMS publishes the same formula in its fee schedule documentation.
Change any one input and the payment moves. A code’s work RVU can be revalued. The practice expense RVUs can be rebuilt. The conversion factor changes every year. For 2026, two of those three inputs moved in ways a single update percentage does not describe, and one of them moved in opposite directions depending on where the service was furnished.
| Input | What it measures | What happened in 2026 |
|---|---|---|
| Work RVU | Physician time, skill, and intensity | Reduced 2.5% for non-time-based codes |
| Practice expense RVU | Clinical staff, supplies, equipment, office costs | Indirect costs reallocated from facility to office settings |
| Malpractice RVU | Professional liability premiums | Updated for 2026; a small share of the total |
| Conversion factor | Turns total RVUs into dollars | Two factors exist for the first time |
Medicare also publishes two practice expense values for most services. The non-facility rate pays for the full range of resources. The facility rate pays only the portion the practitioner incurs while working in a hospital outpatient department, an ambulatory surgical center, or another facility setting. That split is why the same procedure can pay differently in an office and a hospital, and it explains why the 2026 practice expense change lands unevenly.
Two conversion factors, and how the 2026 update is built
For the first time, CMS set two conversion factors. Statutorily, qualifying participants in an advanced alternative payment model receive a different update than everyone else. The 2026 qualifying APM factor is $33.5675, up 3.77 percent. The nonqualifying factor is $33.4009, up 3.26 percent. The 2025 single factor was $32.3465. CMS states both figures in the final rule fact sheet.
Those increases stack from three pieces. A statutory update adds 0.75 percent for qualifying participants and 0.25 percent for everyone else. A one-year 2.50 percent increase under Public Law 119-21, the Working Families Tax Cut legislation, adds another layer. A 0.49 percent adjustment accounts for finalized work RVU changes. The AMA logged 528,827 clinicians who earned qualifying status for 2026, which also carries a 1.88 percent lump sum bonus.
| Component | Qualifying APM (QP) | Nonqualifying APM | Note |
|---|---|---|---|
| Statutory update | +0.75% | +0.25% | Required by statute for CY 2026 |
| One-year legislation increase | +2.50% | +2.50% | Public Law 119-21, CY 2026 only |
| Work RVU adjustment | +0.49% | +0.49% | Accounts for finalized code changes |
| 2026 conversion factor | $33.5675 | $33.4009 | Up 3.77% and 3.26% over 2025 |
How the 2026 qualifying APM factor is built
Source: AMA, 2026 Medicare Physician Payment Schedule final rule summary and analysis.
CY 2026 conversion factors compared
Source: CMS CY 2026 PFS final rule fact sheet.
The other half: a -2.5% cut to work RVUs
The conversion factor went up. For a large set of codes, the work RVU behind the code went down. CMS finalized an efficiency adjustment of -2.5 percent to the work RVUs and intraservice time of non-time-based services, using the five-year Medicare Economic Index productivity adjustment as the measure. CMS describes it in the CY 2026 final rule fact sheet.
Time-based codes are exempt. Evaluation and management visits, care management, behavioral health services, services on the Medicare telehealth list, and maternity codes with a global period of MMM keep their full work RVUs. Everything else was on the table. The ACC counted 8,960 codes on the CMS list subject to the adjustment after the exemptions. CMS intends to apply the adjustment again every three years.
The honest math is harder than one percentage. The efficiency cut reduces the work RVU, which is one of three inputs. Its effect on any single code depends on how much of that code’s value is work, whether it is billed in a facility or an office, and how the change interacts with budget neutrality. The ASNC analysis estimated the adjustment would lower overall payment by about 1 percent for most surgical specialties, radiology, and pathology. A practice can lose ground on a code in a year the headline factor rose.
The efficiency adjustment changes a work RVU, not a payment rate. A work-heavy procedure absorbs most of it. A visit code absorbs none of it. Add the practice expense change on top and two practices in the same specialty can see opposite results on the same service. Model your own top codes rather than the national average.
The practice expense shift between hospital and office
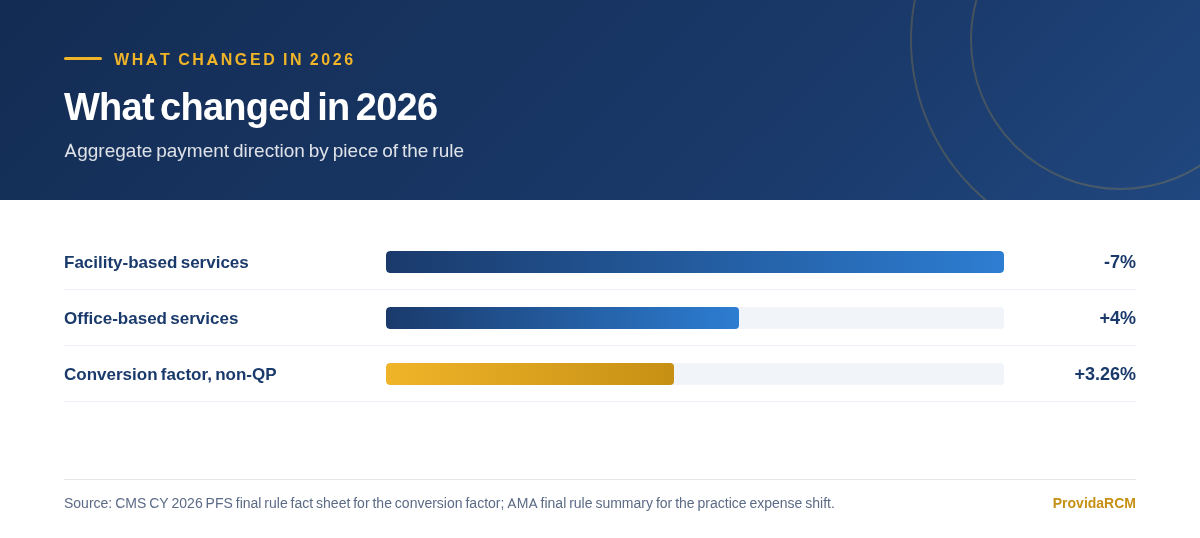
CMS rebuilt how indirect practice expense costs are allocated. The old method assumed a practitioner maintained a separate practice even when working in a hospital, so facility and non-facility services carried indirect costs at the same rate. CMS finalized a change that recognizes higher indirect costs in office settings. In the facility setting, the portion of practice expense allocated by work RVU is cut to half of the non-facility amount. The AMA summary pegs the aggregate effect at about -7 percent for services in facility settings and +4 percent for services in non-facility settings.
Setting dominates the outcome. A cardiologist reading studies in a hospital outpatient department and the same cardiologist reading them in an office do not feel the same 2026 rate. The change was built to correct a distortion, and for a practice that bills mostly in facilities it is a real reduction. For an office-based practice it is a real increase, before the efficiency adjustment is layered on.
| Setting | Direction of the 2026 effect | Approximate aggregate impact | What drives it |
|---|---|---|---|
| Non-facility (office) | Increase | About +4% | Higher indirect cost allocation recognized |
| Facility (hospital, ASC) | Decrease | About -7% | Indirect cost allocated by work RVU is halved |
One more practice expense change matters to a narrower group. CMS now uses auditable hospital cost data from the Medicare outpatient prospective payment system to set relative rates and inform cost assumptions for radiation treatment services and some remote monitoring services. That replaces survey-based assumptions for those codes with data that can be audited year over year.
Supervision and telehealth rules that are now permanent
The biggest operational change in the 2026 rule is not a rate. It is who has to be standing where. CMS made virtual direct supervision permanent. A supervising practitioner can meet the immediately available standard through real-time, two-way audio and video, with no physical presence in the same suite. Audio-only does not qualify. PYA outlines the services covered.
- Incident-to services under 42 CFR 410.26, excluding services with a global surgery indicator of 010 or 090
- Diagnostic tests under 42 CFR 410.32
- Pulmonary rehabilitation under 42 CFR 410.47
- Cardiac and intensive cardiac rehabilitation under 42 CFR 410.49
- Document the technology used and the times the supervising practitioner was available
Teaching physicians gained a permanent virtual presence for resident-furnished telehealth. A three-way audio and video visit with the patient, the resident, and the teaching physician in separate locations satisfies the presence requirement. For in-person resident services, physical presence during the key portion still applies. CMS also permanently removed frequency limits on subsequent inpatient visits, subsequent nursing facility visits, and critical care consultations delivered by telehealth.
The CY 2026 rule carries the FQHC and RHC distant site telehealth pathway, billed under HCPCS G2025, through December 31, 2026. The Consolidated Appropriations Act, 2026 later extended that authority, so confirm the current end date with your Medicare administrative contractor before you build a plan around any single date.
The 2027 proposed rule and the 2.5% cliff
CMS issued the CY 2027 fee schedule proposed rule on July 14, 2026. It proposes the same statutory updates: +0.75 percent for qualifying APM participants and +0.25 percent for everyone else, plus a 0.53 percent adjustment for proposed work RVU changes. Then the important part. The one-year 2.50 percent increase from 2026 expires. The CMS fact sheet states that current law requires a -2.50 percent reduction in Medicare payment compared with CY 2026.
No final 2027 conversion factor exists yet, and the rule is still proposed, so no practice should bank a number. The direction is what matters for planning. The one-time increase that lifted 2026 does not repeat, and the efficiency adjustment and practice expense changes finalized for 2026 carry forward unless CMS changes them.
The comment period closed on September 14, 2026, and specialty societies used it. Whatever CMS finalizes in the CY 2027 rule lands in January 2027 rates. If your 2026 budget leaned on the one-time increase, the 2027 planning assumption should be a flat-to-down year on Medicare rates.
One more 2027 change matters to a narrower group. The 2026 final rule also created the Ambulatory Specialty Model, a mandatory two-sided risk model for cardiologists treating heart failure and for pain, neurosurgery, orthopedic, and rehabilitation specialists treating low back pain. It starts January 1, 2027 in selected markets, runs five performance years, and offers no opt-out. The legal analysis from JD Supra summarizes who is included.
What to check in your own fee schedule files
A national update percentage is not a payment forecast. Your realized rates move with your code mix, your setting, your locality GPCI, and your payer contracts. The 2026 changes widen that gap, because the work RVU adjustment and the practice expense shift hit different codes in different directions.
- Pull the 2026 RVU file and compare work, practice expense, and total RVUs against 2025 for your top 25 codes by volume
- Separate your facility-billed codes from your office-billed codes before you read the update
- Re-run your top codes through the local GPCIs, not the national factor on its own
- Flag any code that lost work RVU value and check whether a payer contract is tied to a percentage of Medicare
- Confirm which supervising practitioners can now be virtual, and update the documentation standard
Payers that peg reimbursement to a percentage of Medicare inherit the change automatically, which cuts both ways. The work runs through your billing and coding operations: keeping medical billing aligned with the current RVU files, checking that medical coding reflects the revalued codes, and watching the cash through AR management. If a payer’s posted allowables drift from the 2026 factor, the denial management team usually sees it first as a pattern of underpaid claims.
Rate changes are a coding accuracy problem before they become a collections problem. If your top codes crossed a revaluation and nobody updated the charge master or the payer fee schedules, the loss shows up as a slow drift, not an error anyone flags. A quarterly fee schedule reconciliation catches it early.
Questions practices ask us about this
What is the conversion factor for the Medicare Physician Fee Schedule in 2026?
It is $33.4009 for practitioners who are not qualifying APM participants, a 3.26 percent increase over the 2025 factor of $32.3465. Qualifying APM participants get $33.5675, a 3.77 percent increase. Both figures come from the CY 2026 final rule and reflect a statutory update, a one-year 2.50 percent increase, and a 0.49 percent work RVU adjustment. Medicare then applies geographic practice cost indices by locality.
Did Medicare rates go up or down in 2026?
The conversion factor went up, but that is not the same as every rate going up. The work RVU efficiency adjustment reduced the value of thousands of non-time-based codes by 2.5 percent, and the practice expense change cut facility-based payments by roughly 7 percent while raising non-facility payments by about 4 percent. Whether your practice gained or lost depends on your code mix and where you bill.
What is the work RVU efficiency adjustment?
It is a -2.5 percent reduction to the work RVUs and intraservice time of non-time-based services, set using the five-year Medicare Economic Index productivity adjustment. CMS applies it to codes whose value it believes can fall as practitioners gain experience. Evaluation and management visits, care management, behavioral health, telehealth, and maternity codes are exempt. CMS intends to apply the adjustment again every three years.
Can a supervising physician be remote under the 2026 rules?
Yes, for many services. CMS made virtual direct supervision permanent, allowing a supervising practitioner to be immediately available through real-time, two-way audio and video rather than physically present in the suite. Audio-only does not qualify. The policy covers incident-to services and certain cardiac, pulmonary, and diagnostic services, but not services with a global surgery indicator of 010 or 090.
What did the CY 2027 proposed rule say about the conversion factor?
The proposed rule, issued July 14, 2026, proposes the same statutory updates: +0.75 percent for qualifying APM participants and +0.25 percent for everyone else, plus a 0.53 percent work RVU adjustment. Because the one-year 2.50 percent increase from 2026 expires, CMS states current law would reduce Medicare payment by 2.50 percent compared with 2026. No final 2027 conversion factor has been set.
Does the 2026 update apply to commercial payer contracts?
Only if the contract is written that way. Commercial rates tied to a percentage of Medicare inherit the conversion factor and RVU changes automatically, including the reductions. Contracts with fixed fee schedules or annual escalators do not move with Medicare. That is why a practice can see Medicare rates hold while a Medicare-linked commercial line falls, or the reverse.
Want this fixed in your practice?
We run full-cycle billing, coding, credentialing and denial work for practices across the country. Send us a few months of claims and we will show you where the money is going.
Book a free billing review- CMS, Calendar Year (CY) 2026 Medicare Physician Fee Schedule Final Rule fact sheet (CMS-1832-F). cms.gov/newsroom/fact-sheets/calendar-year-cy-2026-medicare-physician-fee-schedule-final-rule-cms-1832-f
- Federal Register, CY 2026 Payment Policies Under the Physician Fee Schedule, final rule, 90 FR 49266. federalregister.gov/documents/2025/11/05/2025-19787/medicare-and-medicaid-programs-cy-2026-payment-policies-under-the-physician-fee-schedule-and-other
- CMS, Calendar Year (CY) 2027 Medicare Physician Fee Schedule Proposed Rule fact sheet. cms.gov/newsroom/fact-sheets/calendar-year-cy-2027-medicare-physician-fee-schedule-proposed-rule
- Federal Register, CY 2027 Payment Policies Under the Physician Fee Schedule, proposed rule (CMS-1848-P). federalregister.gov/documents/2026/07/16/2026-14327/medicare-and-medicaid-programs-cy-2027-payment-policies-under-the-physician-fee-schedule-and-other
- AMA, 2026 Medicare Physician Payment Schedule and Quality Payment Program final rule summary and analysis. ama-assn.org/system/files/2026-mpfs-final-rule-summary-analysis.pdf
- CMS, Medicare physician fee schedule documentation, payment formula and geographic practice cost indices. cms.gov/medicare/physician-fee-schedule/search/documentation
- American College of Cardiology, Efficiency Adjustment Explainer, 2026 Medicare PFS. acc.org/latest-in-cardiology/articles/2025/07/31/18/08/efficiency-adjustment-explainer-2026-medicare-pfs-proposed-rule
- American Society of Nuclear Cardiology, analysis of policy changes in the 2026 fee schedule. asnc.org/news/asnc-analysis-policy-changes-in-2026-fee-schedule-proposed-rule
- PYA, 2026 MPFS final rule, virtual direct supervision and teaching physician requirements. pyapc.com/insights/navigating-permanent-changes-to-direct-supervision-and-teaching-physician-requirements
- CMS, MM14315 Medicare Physician Fee Schedule Final Rule Summary, CY 2026. cms.gov/files/document/mm14315-medicare-physician-fee-schedule-final-rule-summary-cy-2026.pdf
- JD Supra, CMS finalizes mandatory Ambulatory Specialty Model for heart failure and low back pain specialists. jdsupra.com/legalnews/cms-finalizes-mandatory-ambulatory-9088591
- CMS, MM14468 Billing of Distant Site Telehealth Services in Rural Health Clinics and Federally Qualified Health Centers. cms.gov/files/document/mm14468-rural-health-clinics-federally-qualified-health-centers-billing-distant-site-telehealth.pdf


