

Payer takebacks are money a payer recoups after it already paid the claim. They arrive as one of three things: a repayment demand, a recoupment that withholds future payments, or a post-payment review finding from a recovery auditor. Each letter carries its own authority, its own clock and its own appeal route.
What a payer takeback is, and the three letters that start one
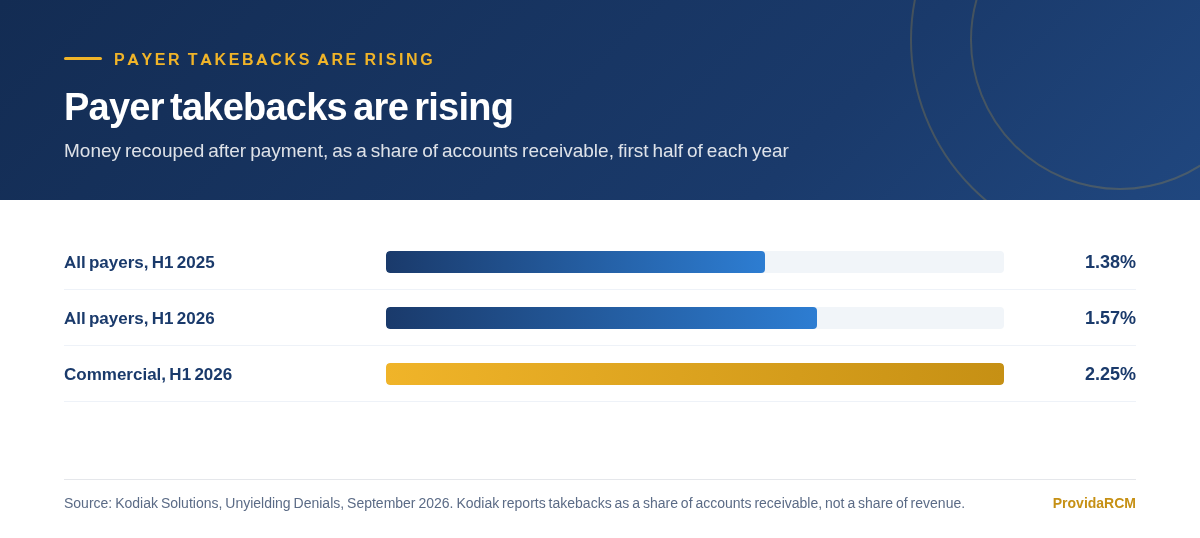
A takeback is money a payer already paid and then recovered. Kodiak Solutions tracks the number across more than 2,300 hospitals and 375,000 physicians on its platform, and it reports takebacks as a share of accounts receivable. The first-half 2026 reading was 1.57%, up from 1.38% a year earlier. That base matters, because this is not a percentage of revenue.
Three documents do the work, and they are not interchangeable. A demand letter states that an overpayment exists and asks for repayment. A recoupment withholds future Medicare payments to satisfy the debt. A recovery auditor demand is a demand letter that follows a post-payment review of the record. The first is a bill, the second is a collection action, and the third is a finding.
| Document | Who issues it | What it lets the payer do | Its limit |
|---|---|---|---|
| Demand letter | Medicare contractor, MAC or a commercial payer | State an amount owed and require repayment | Interest starts only if the debt is unpaid after 30 days (CMS MLN006379) |
| Recoupment, also called offset | Medicare contractor | Withhold future payments to satisfy the debt | Cannot begin before day 41 from the demand, and stops on a timely appeal (42 CFR 405.379) |
| Recovery auditor demand | A post-payment review contractor | Run the same demand and recoupment machinery, after reviewing the record | The finding is a coverage or documentation determination, appealed at redetermination |
| Commercial payer offset | The payer, under the participation agreement | Offset future claims if the contract grants that right | Set by contract language, not by 42 CFR Part 405 |
Everything on this page about day 41, rebuttals and reopening windows comes from 42 CFR Part 405 and applies to Medicare fee-for-service. A commercial payer’s right to take money back lives in your participation agreement. Read that contract for the offset clause and the audit lookback period, and do not assume the Medicare numbers carry over.
How a post-payment audit finds that a paid claim was wrong
An audit that happens after payment reads the record, not the claim form. The reviewer asks whether the documentation supports the service that was billed, and whether the payer was the right payer for that date of service. A finding then travels back through the demand and recoupment machinery described above, which is why the paperwork is the same whether the money came from a routine claims review or a recovery auditor.
Five findings cause most of the money that comes back. They are not equally defensible on appeal, and they do not share a single owner.
| Finding | Why it shows up after payment | Where the basis sits | Who owns the fix |
|---|---|---|---|
| Documentation or medical necessity | The reviewer read the note and could not find the necessity the claim implied | CARC 50 and the payer’s own coverage policy | Clinical documentation and coding |
| Coding | A diagnosis or procedure code did not survive review, or a bundling edit was applied late | CARC 11 and CARC 97 | Coding |
| Eligibility discovered later | Coverage had ended, or the patient had another primary plan, and no one caught it at the desk | CMS Medicare Financial Management Manual, Chapter 3 | Front end |
| Duplicate payment | The same service was paid twice | CARC 18; a duplicate-claim denial is a clerical error handled as a reopening (42 CFR 405.980) | Billing operations |
| Coordination of benefits order changed | A plan that was secondary became primary, so the original payment was wrong from the start | CARC 22; MSP recovery meeting 42 CFR 405.379(b) is subject to the recoupment limit | Front end and payer relations |
CARC 15, the retired authorization-number code, was deactivated on 1 May 2018 and still appears in denial reports and vendor posts as though it were current. The live codes for that failure are CARC 197 when no authorization exists, CARC 284 when the number does not match the billed service, and CARC 296 when it does not match the provider. CARC 50 covers medical necessity, CARC 29 covers an expired filing limit, and CARC 18 covers an exact duplicate. Verify any code against the current X12 list before you cite it.
What the demand letter has to contain
A Medicare demand letter is not a summary. It is a document with required content, and when a field is missing, the demand itself is the thing you challenge rather than the finding.
- That an overpayment was made, and the exact amount
- How the overpayment was calculated
- The patient’s name and Medicare Beneficiary Identifier
- The dates and types of services that were overpaid
- How interest accrues and the rate, if the debt is unpaid after 30 days
- The extended repayment schedule option, in writing
- How recoupment works, when it starts, and the effect of filing an appeal
- Rebuttal rights and administrative appeal rights
The contractor must also give you an opportunity for rebuttal, and the CMS Medicare Overpayments fact sheet puts that window at 15 calendar days from the date of the demand letter. A rebuttal is a statement and evidence explaining why recoupment should not start. Filing one does not, by itself, stop recoupment.
The MAC should also tell you whether the overpayment falls inside the recoupment limitation at 42 CFR 405.379. Cost report overpayments, most secondary-payer recoveries beyond the types listed in that section, and beneficiary overpayments sit outside it. If a demand does not identify its basis, that omission is worth a written question before you decide anything else.
The Medicare clock: the windows that decide whether you keep the money
You have 120 calendar days from receipt of the initial determination to request a redetermination, and the regulation presumes you received it five days after the notice date (42 CFR 405.942). Waiting the full 120 days costs money. To limit recoupment, the request has to reach the contractor within 30 days of the demand letter.
The Medicare recoupment clock, in days from the demand letter
Sources: 42 CFR 405.373 through 405.379; CMS Medicare Overpayments fact sheet (MLN006379); CMS transmittal R141FM.
Under 42 CFR 405.379, a contractor can begin recoupment no earlier than 41 days from the initial overpayment demand, but must stop, or never start, once it receives a timely and valid redetermination request. A reconsideration by the qualified independent contractor, filed within 180 days of the redetermination notice under 42 CFR 405.962, halts recoupment again. Recoupment resumes only after a decision.
Reopening is the other limit, and it caps how far back a claim can be revisited. A contractor may reopen an initial determination within one year for any reason, within four years for good cause, and at any time where there is reliable evidence of fraud or similar fault (42 CFR 405.980). A practice can request a reopening on the same one-year and four-year terms. Third-party payer error is not a clerical error, so it opens no shortcut.
Repayment options when the finding stands
Once a finding holds, the CMS fact sheet lists several responses to a demand letter, and each carries a different cost.
- Pay in full. The debt stops accruing interest and nothing else is required.
- Request immediate recoupment. The contractor offsets against future payments, and MMA section 935 keeps that voluntary repayment out of the interest calculation.
- Let standard recoupment run. It starts on the contractor’s schedule and interest accrues on the unpaid balance.
- Request an extended repayment schedule, or appeal by asking for a redetermination. Each one stops a different clock.
An extended repayment schedule is the option most practices underuse. Under 42 CFR 401.607, installment debts are normally liquidated in three years or less. Hardship is defined there as outstanding overpayments not already in an approved schedule equal to 10% or more of your total Medicare payments for the prior cost reporting period or calendar year, and extreme hardship opens a plan the statute allows to run as long as 60 months (42 U.S.C. 1395ddd(f)(1)(A)).
Interest is the reason to move first. The fact sheet states that if the overpayment is not fully paid within 30 days of the initial demand letter, simple interest begins on day 31 on the outstanding principal balance. If you win on appeal, money already recouped comes back with interest payable to you under 42 U.S.C. 1395ddd(f)(2)(B).
An extended repayment schedule moves the money, not the finding. Interest keeps accruing on the unpaid balance unless a timely appeal already halted recoupment. If you believe the finding is wrong, the appeal is the cheaper path and the schedule is the fallback.
How to tell a demand you should contest from one you should pay
A valid demand names the patient, the dates, the services and the calculation. A demand that fails to do any of that is worth contesting on its face, because the contractor has to identify the overpayment clearly enough for you to respond to it.
Past the paperwork, the question is whether the finding is defensible on the record.
- Does the demand identify the patient, dates, services and calculation, or is it a lump sum? Contest the shape first.
- Is the code on the demand current on the X12 list, or is it a retired code such as CARC 15? A retired code means the finding was mapped wrong.
- Did an authorization or a clinical note exist that the reviewer never saw? That is usually a redetermination with the documentation attached.
- Was the service defensible against the payer’s own written policy? If the note answers the policy, appeal it. If it does not, do not.
- Is the amount large enough to carry the appeal? Some small findings with a clean record are cheaper to repay than to argue.
We handle this work inside denial management, on top of the same medical billing and AR management teams that scrub claims before they go out. When takebacks concentrate in one payer, a denial code review of the last two quarters usually shows whether the problem sits in documentation or in coding.
Why payer takebacks cost more than a denial did
A denial never becomes revenue. A takeback reverses revenue you already booked, reported and probably spent. That is the whole difference, and the Kodiak figures show how wide the gap has become between money going out and money coming back.
Takebacks against post-payment recoveries, share of accounts receivable
Source: Kodiak Solutions, Unyielding Denials, September 2026. Both metrics are a share of accounts receivable, not a share of revenue.
Read the two lines together. Takebacks as a share of accounts receivable moved from 1.38% to 1.57%, a 13.8% increase, while post-payment recoveries fell from 2.48% to 2.21%, a 12.2% decrease. Providers are being taken back more often and winning back less of what was taken when they appeal.
The pressure is not uniform across payers. Kodiak’s own analysis reports Medicare Advantage takebacks at more than double the traditional Medicare rate, and commercial takebacks at 2.25% of accounts receivable, up 12%. The commercial final denial rate rose 9.1% to 2.89% of accounts receivable over the same period, even as the initial denial rate for those claims fell.
That last pair is the trap for a practice watching only its denial rate. Initial denials fall, the dashboard looks better, and the takebacks land two quarters later against money that was already counted. Track takebacks as a share of accounts receivable on their own line, broken out by payer. Net collection rate shares the same blind spot, because it is calculated after the money is booked.
Post-payment findings are contested on the same grounds as any denial: medical necessity, a secondary payer order that changed underneath the claim, an authorization the reviewer never saw. The appeal letter is the same letter. What differs is the deadline, and the fact that recoupment may already be running while you write it.
Questions practices ask us about this
What is a payer takeback?
Money a payer recoups after it already paid a claim. Kodiak Solutions calls it a takeback and reports it as a share of accounts receivable: 1.57% in the first half of 2026, up from 1.38% a year earlier. It is not a denial, because the claim was paid and the revenue was booked before the money came back.
How long does a practice have to respond to a Medicare overpayment demand?
The demand comes from your MAC, and the windows differ by what you are doing. A rebuttal is due within 15 calendar days of the demand letter. To limit recoupment, a valid redetermination request has to reach the contractor within 30 days, although you have up to 120 calendar days from receipt of the initial determination to appeal at all (42 CFR 405.942).
Does filing an appeal stop Medicare recoupment?
A timely and valid request does. Under 42 CFR 405.379, the contractor can begin recoupment no earlier than day 41 from the demand letter, but must stop, or never start, once it receives a valid redetermination request. A reconsideration by the qualified independent contractor stops it again. File inside 30 days of the demand letter if the goal is to hold the cash.
How far back can Medicare reopen a paid claim?
A contractor may reopen an initial determination within one year for any reason, within four years for good cause, and at any time where there is reliable evidence of fraud or similar fault (42 CFR 405.980). A practice can request a reopening on the same one-year and four-year terms. Third-party payer error is not a clerical error, so it opens no shortcut.
What is the difference between a rebuttal and an appeal?
A rebuttal is a statement and evidence explaining why recoupment should not begin, filed within 15 calendar days of the demand letter under 42 CFR 405.374. Filing one does not stop recoupment. An appeal is a request for a redetermination of the overpayment determination itself, and a timely one does stop recoupment. A rebuttal questions the collection. An appeal questions the finding.
Can a practice get an extended repayment schedule for an overpayment?
Yes. Under 42 CFR 401.607(c), installment debts are normally liquidated in three years or less, and hardship is defined as outstanding overpayments equal to 10% or more of your total Medicare payments for the prior cost reporting period or calendar year. Extreme hardship opens a plan the statute allows to run as long as 60 months (42 U.S.C. 1395ddd(f)(1)(A)).
Are takebacks hitting your A/R?
We run denial management, appeals and AR follow-up for practices across the country, and we report takebacks as a share of accounts receivable by payer. Send us two quarters of remittances and we will show you where the money is leaving.
Book a free billing review- 42 CFR 405.371, Suspension, offset, and recoupment of Medicare payments to providers and suppliers. law.cornell.edu/cfr/text/42/405.371
- 42 CFR 405.373, Proceeding for offset or recoupment, and 42 CFR 405.374, Opportunity for rebuttal. law.cornell.edu/cfr/text/42/405.373
- 42 CFR 405.379, Limitation on recoupment of provider and supplier overpayments. law.cornell.edu/cfr/text/42/405.379
- 42 CFR 405.980, Reopening of initial determinations, redeterminations, reconsiderations, decisions, and reviews. law.cornell.edu/cfr/text/42/405.980
- 42 CFR 405.942, Time frame for filing a request for a redetermination. law.cornell.edu/cfr/text/42/405.942
- 42 CFR 401.607(c), Claims collection, installment payments and extended repayment schedules. law.cornell.edu/cfr/text/42/401.607
- CMS Medicare Overpayments fact sheet, MLN006379. cms.gov/files/document/medicare-overpayments.pdf
- CMS Medicare Financial Management Manual, Chapter 3, overpayments and demand letter content. cms.gov/regulations-and-guidance/guidance/manuals/downloads/fin106c03.pdf
- CMS transmittal R141FM, Limitation on recoupment (MMA section 935) for provider and supplier overpayments. cms.gov/regulations-and-guidance/guidance/transmittals/downloads/r141fm.pdf
- CMS Medicare Claims Processing Manual, Chapter 29, appeals of claims decisions. cms.gov/regulations-and-guidance/guidance/manuals/downloads/clm104c29.pdf
- X12, Claim Adjustment Reason Codes, current and deactivated list. x12.org/codes/claim-adjustment-reason-codes
- Kodiak Solutions, Unyielding Denials, September 2026 analysis of takebacks as a share of accounts receivable. go.kodiaksolutions.io/kpi_august_2026


