

Charge capture leakage is care your practice delivered and never billed: the visit with no note, the drug nobody charged for, the report that named more than the ticket captured. It never shows up as a denial, because a service that was never billed cannot be denied. It shows up as money you never knew you had.
What charge capture leakage actually is
Leakage is the gap between care that was delivered and care that reached a claim. A nurse starts an IV, a provider reviews an outside scan, a weekend rounding note goes into the chart, and none of it lands on a charge ticket. Nothing is denied, because nothing was billed. The revenue never appears on a remittance advice, an aging report or a denial log.
That silence is what makes leakage different from a denial. A denied claim generates a code, a letter and a deadline, so someone eventually works it. A missed charge generates nothing. It is invisible in every system that only tracks what was submitted.
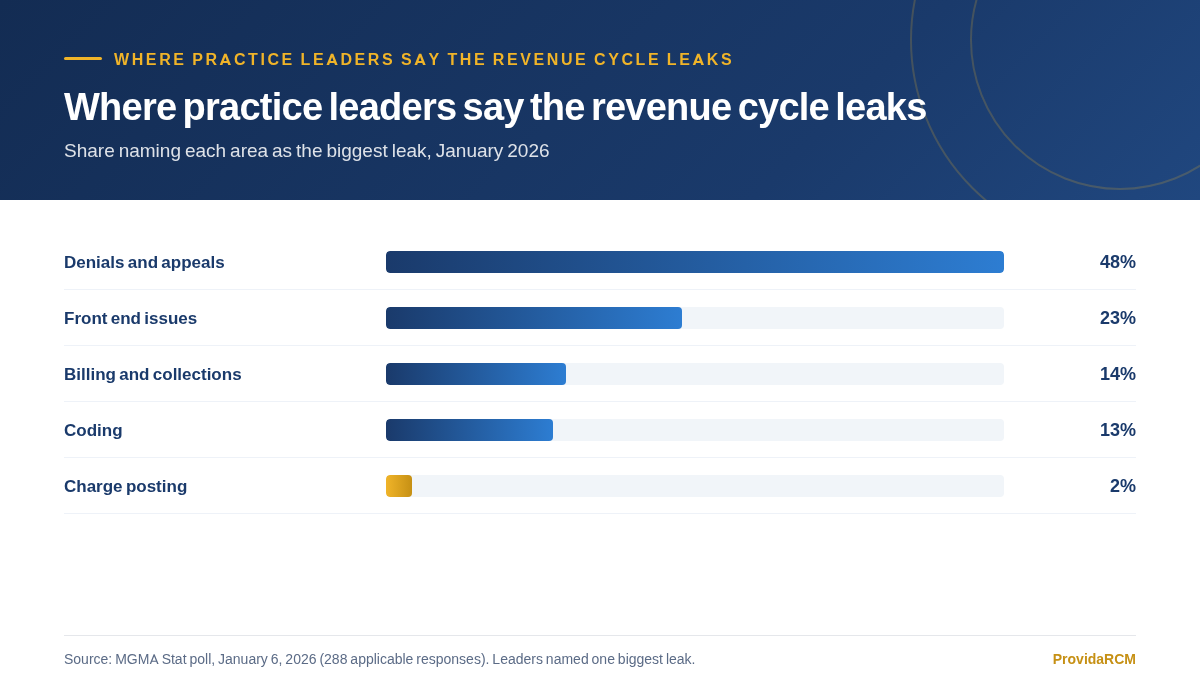
MGMA’s January 6, 2026 Stat poll asked practice leaders where their revenue cycle leaks most. Denials and appeals came first at 48%, front end issues at 23%, billing and collections at 14%, coding at 13%, and charge posting at 2% (MGMA Stat). Charge posting sitting last is the symptom, not the reassurance. A leak that never produces a line item cannot be named in a poll either.
| Problem | What happened | Where it shows up | Who owns it |
|---|---|---|---|
| Charge capture leakage | Care was delivered and never billed | Nowhere until someone reconciles counts | Clinical team and charge entry |
| Denial | Care was billed and the payer refused it | A CARC code on the 835 remittance | Billing and coding |
| Takeback | Care was paid and the payer recouped it | A negative adjustment after payment | Billing and appeals |
| Contractual write-off | Care was billed and paid below charge | A CO-45 adjustment you agreed to | Nobody. It is the contract |
Leakage cannot be found in a report built from claims, because the missing items are missing from the claims. It is found by counting something upstream and comparing it to the claim count. Scheduled visits, arrived visits, documented notes and coded encounters are the counts that matter.
Where the leaks actually sit
Seven spots account for most of the leakage in a physician practice. Each one is a place where a real service stops short of a billable line, and each has a different owner. The table below maps them.
| Leak point | What it looks like | Control that catches it | Owner |
|---|---|---|---|
| In-room service off the ticket | A procedure, injection or screening done in the room but not written on the encounter form | Scheduled-to-billed reconciliation by service line | Clinical team |
| Drugs and supplies not charged | A vial, a tray or a brace opened for the patient and absent from the charge | Supply and drug log checked against administration notes | Charge entry |
| Ancillary work in another department | A lab draw, an EKG or imaging done down the hall, never captured to the visit | Department charge log reconciled to the encounter | Ancillary department |
| Documented but never signed or released | The note exists in the chart and coding never sees it | Unsigned and unreleased note report, checked daily | Provider and coding |
| Operative report names more than the ticket | The dictation lists a second procedure the charge ticket does not | Report-to-charge review on high-volume case types | Coding |
| After-hours and weekend work | Rounding notes, calls and bedside procedures outside the posted schedule | On-call and weekend log reconciled to charges | Clinical team |
| Level of service below the documentation | 99213 billed when the note supports 99214 | Documentation-to-level audit on a monthly sample | Coding |
Two of the seven get underestimated because they involve small items. One dose of a drug, a catheter tray or a brace looks trivial on its own. The same item missing from a few hundred encounters a year does not. Ancillary work follows the same pattern: a lab draw or an EKG performed in another department depends on that department’s log reaching the visit charge.
The operative report is the classic mismatch. A dictation and a charge ticket are built by two different people at two different times, and a second procedure the surgeon describes in the narrative can be absent from the ticket. Review the report against captured charges for your highest-volume case types, on a small sample every month rather than a large one once a year.
Systematic undercoding is the quietest item on the list. MGMA’s January 2026 Stat article names widespread undercoding, especially on E/M visits, as a coding contributor, driven by limited provider training and documentation gaps. Downcoding is real and measurably common: the OIG’s medical record review of 2010 E/M claims found 42% were incorrectly coded, a category the OIG defines to include billing below the level the documentation supports (OEI-04-10-00181).
Why 2010 E/M claims failed review
Source: HHS Office of Inspector General, OEI-04-10-00181 (2014), medical record review of a random sample of 2010 Part B E/M claims. Incorrect coding includes both upcoding and downcoding.
The reconciliation that catches each one
Every leak in that table is found the same way: count something upstream and compare it to a downstream count. Build one line that runs scheduled, arrived, documented, coded, billed, and require every gap between two columns to be explained. A gap nobody can explain is a leak with a name attached to it.
- 01
Scheduled against arrived
Pull the appointment schedule for the period and the arrival log. Check every no-show and cancellation for a rescheduled visit, because a patient who was never rebooked never generates a charge at all.
- 02
Arrived against documented
Match the arrival list to signed notes. A visit with no note is either an unrecorded encounter or one that should not have been billed. Both need an answer, and the answer is different.
- 03
Documented against coded
Match signed notes to encounters released to coding. Notes that sit unsigned or unreleased are the most common reason a delivered service never reaches a coder’s queue.
- 04
Coded against billed
Compare coded encounters to claims sent. A coded encounter that was never billed is a charge sitting in a queue while a filing clock runs.
- 05
Billed against expected
Compare the billed service mix to your own history by provider and service line. A provider whose level mix drifts down while the documentation does not is the signal to audit.
| Stage | Count | What disappears at this step | Control |
|---|---|---|---|
| Scheduled | 1,000 | 60 patients who were never rebooked | Recall list |
| Arrived | 940 | 38 visits with no signed note | Unsigned note report |
| Documented | 902 | 41 notes held or not released to coding | Release queue review |
| Coded | 861 | 16 coded encounters never sent | Billed versus coded check |
| Billed | 845 | Nothing. This is the end of the line | Charge lag report |
Scheduled 1,000, billed 845, so 155 encounters left the pipeline before a claim existed. At an average allowed amount of $92, that is about $14,260 in a month that never appears on a denial report, because no claim was ever submitted to deny.
The documented-to-coded step deserves its own attention, because a note that is never signed is not a billable record. CMS states that it requires a signature for two purposes: to satisfy a specific signature requirement in statute, regulation or coverage policy, and to resolve authenticity concerns about the documentation (MLN905364). The scale is not small.
CMS reports that insufficient documentation is one of the two categories making up the majority of Medicare fee-for-service improper payments, and that it accounted for 79.11% of 2024 Medicaid improper payments and 61.56% of CHIP improper payments (CMS FY 2024 fact sheet).
Insufficient documentation as a share of 2024 improper payments
Source: CMS, Fiscal Year 2024 Improper Payments Fact Sheet. Each figure is the share of that program’s improper payments caused by insufficient documentation in the reporting period, not a leakage rate.
Charge lag and the variance review
Charge lag is the number of days between the date of service and the date the charge is entered. It is one of the more useful early warnings of a missed charge, because a ticket that sits for a week is a ticket nobody remembers. Report it two ways: by provider and by service line, because the two views catch different failures.
A provider-level lag report is uncomfortable and effective. It shows which clinicians close their encounters the same day and which let a week pass. The service-line view catches a different problem: one department or location that falls behind every period, which usually points to a manual log, a missing interface or a person who is out.
| Report | What it shows | Cadence | Owner |
|---|---|---|---|
| Scheduled-to-billed reconciliation | Every gap between a visit that was scheduled and a claim that was sent | Monthly | Billing manager |
| Charge lag by provider | Days from service to charge entry, per clinician | Weekly | Billing manager |
| Charge lag by service line | Which department or location falls behind | Weekly | Revenue integrity |
| Unsigned and unreleased notes | Notes that exist but no coder has seen | Daily | Coding lead |
| Variance review | Dollar difference between expected and billed charges, by service line | Weekly | Named clinical owner |
The variance review is where a number becomes a decision. Compare expected charges, built from the schedule and the procedure mix, to billed charges for the same period. Put a named owner on each line, and make it the clinical lead for that service line rather than the billing office. The fix usually sits in the room, so that person should hold the variance.
A variance review owned by a committee has no owner. Name the clinician or manager responsible for each service line, hand them the dollar variance, and hold the review on the same day every week. A recurring meeting with a named owner closes gaps that a monthly report cannot.
Hard stops inside the record
Reports find leakage after it happens. Hard stops prevent it. A hard stop is a rule the practice sets inside the record that will not let an encounter close until the common misses have an answer.
- Refuse to close an operative encounter until the surgeon states whether a second procedure was performed
- Require an answer when a scheduled visit has no note by the end of the next business day
- Flag any encounter where a drug or supply was documented as administered but no code was entered
- Block release of a note with no signature, and route it to the provider nightly
- Require a reason in the note when a visit is billed below the practice median for that provider
- Alert when an ancillary order exists with no matching charge within 24 hours
- List unsigned notes older than 72 hours on the daily huddle sheet
| Metric | What it tells you | Warning sign | Cadence |
|---|---|---|---|
| Scheduled-to-billed conversion | Whether every delivered visit reaches a claim | Any month below your own six-month average | Monthly |
| Charge lag by provider | How fast charges are captured, per clinician | A provider above the practice median two months running | Weekly |
| Charge lag by service line | Where a department is falling behind | One line lagging the others every period | Weekly |
| Unsigned notes older than 72 hours | Notes that cannot be coded or billed | A count that is not falling after a fix | Daily |
| Missing-charge variance | The dollar value of gaps you cannot explain | A variance you cannot tie to payer policy | Weekly |
| Level-of-service mix by provider | Whether levels are drifting below the documentation | A sustained drop with no change in case mix | Monthly |
Track these for two quarters before you judge them. A single month is noise, and a control that lands perfectly in month one is usually a control that is being worked around by month three. The value of the series is the direction, not the reading.
A real leak or a coding policy choice
Not every unbilled service is a leak. Some are decisions, and treating a decision as a failure wastes the team’s time and weakens trust in the report. Three questions separate the two, and they take less time to answer than the argument they prevent.
- Is it deliberate and written down? A policy that says the practice does not bill one code for one payer is a choice, not a leak, and it should live in a document.
- Is it payer-specific? A service billed to every payer except one points to a coverage rule. The same service missing across every payer points to a process.
- Does it appear on the count? If the reconciliation shows the encounter and the count matches, it was accounted for. If it cannot be found anywhere, it is a leak.
Downcoding is a real leak when it happens by default rather than by policy. A practice that audits its level mix and finds a written reason for a lower level is managing a policy. A practice that finds no reason at all is losing money quietly, and it will never see it on a remittance advice.
Start with one service line and one month. The same discipline that lifts your clean claim rate at submission is what recovers the charges that never reached a claim. If charge lag is the symptom, A/R aging and days in A/R show the downstream cost, and a revenue cycle health check will tell you which of these counts is furthest off in your practice.
Questions practices ask us about this
What is charge capture leakage?
It is care your practice delivered and never billed. A service performed in the room that was left off the encounter form, a drug administered but not charged, an ancillary study done in another department, or a note that was never signed and released to coding all qualify. Nothing is denied, because no claim was created, so the loss never appears on a denial report or an aging report.
How is charge capture leakage different from a denied claim?
A denial means the care was billed and the payer refused it, which produces a claim adjustment reason code and a filing deadline for your team to work. Leakage means the care never became a claim at all, so no code, letter or deadline exists. That difference matters for ownership: denials belong to billing and coding, while leakage usually belongs to the clinical team, charge entry or a department outside the billing office.
How do we find missed charges in our own practice?
Run a five-stage count for one period: scheduled, arrived, documented, coded, billed. Take your appointment schedule, your arrival log, your signed notes, your coding queue and your submitted claims, then require an explanation for every gap between two stages. The explanation is the finding, and it usually names the owner of the fix in the same sentence.
How long should charge entry take after a visit?
There is no single national number, so set your own internal target and report against it by provider. The useful rule is that the target should be short enough that the person entering the charge still remembers the encounter. Measure the days from date of service to charge entry, publish the distribution by clinician every week, and treat a rising tail as the early warning it is.
What is charge lag and why does it matter?
Charge lag is the number of days between the date of service and the date the charge is entered into the system. Long lag is a leading indicator of missed charges, because details fade and tickets get set aside. It also pushes claims toward payer filing limits, which is why a lagged charge can become a timely filing write-off instead of revenue. Report it by provider and by service line.
Does systematic undercoding count as charge capture leakage?
Yes, when it is not a deliberate policy. Billing a lower level of service than the documentation supports is still delivering care and collecting less than the record supports for it. The OIG’s medical record review of 2010 E/M claims found 42% were incorrectly coded, a category that includes downcoding as well as upcoding. Audit your level mix by provider, and write down any policy that explains a lower level.
Want this fixed in your practice?
We run full-cycle billing, coding, credentialing and denial work for practices across the country. Send us a few months of claims and we will show you where the money is going.
Book a free billing review- HHS Office of Inspector General, Improper Payments for Evaluation and Management Services Cost Medicare Billions in 2010 (OEI-04-10-00181), 2014. oig.hhs.gov/reports/all/2014/improper-payments-for-evaluation-and-management-services-cost-medicare-billions-in-2010
- HHS Office of Inspector General, Coding Trends of Medicare Evaluation and Management Services (OEI-04-10-00180), 2012. oig.hhs.gov/reports/all/2012/coding-trends-of-medicare-evaluation-and-management-services
- CMS, Fiscal Year 2024 Improper Payments Fact Sheet, November 2024. cms.gov/newsroom/fact-sheets/fiscal-year-2024-improper-payments-fact-sheet
- CMS Medicare Learning Network, MLN905364 Complying with Medicare Signature Requirements, July 2025. cms.gov/files/document/mln905364-complying-medicare-signature-requirements.pdf
- HFMA, Capturing All Charges: the Operational Reality. hfma.org/revenue-cycle/charge-capture/capturing-all-charges-the-operational-reality
- HFMA, Avoiding the High Cost of High-Capture Leakage. hfma.org/revenue-cycle/charge-capture/55358
- MGMA Stat, Detecting and fixing leaks across the revenue cycle, January 6, 2026. mgma.com/mgma-stat/detecting-and-fixing-leaks-across-the-revenue-cycle


