

A practice financial reporting pack that an owner actually reads is five lines long. How much work got billed. How much of it got collected. How much is sitting past 90 days. How much was denied. How much cleared the front end clean. Everything else is a backup tab, and the meeting that reads the page should run on decisions rather than commentary.
The five lines on the one-page practice financial reporting pack
Ask ten practice owners what their billing service sends each month and most describe a packet nobody finishes. A report built to be read fits on one page and repeats the same lines in the same order, because the information sits in the change between months.
The reason to build that discipline now is margin. In a June 23, 2026, MGMA Stat poll of 251 medical groups, 84% reported year-to-date operating costs higher than at the same point in 2025, 8% said costs were about the same and 8% reported a decrease (MGMA Stat, operating costs keep climbing).
Year-to-date operating costs against the same point in 2025
Source: MGMA Stat poll, June 23, 2026, 251 applicable responses. Share of respondents.
| Number | The line on the page | The decision it drives | Source of truth |
|---|---|---|---|
| 1. Volume | Encounters closed and charged, plus charges | Whether revenue moved on volume or rate, and whether capacity changes | Charge summary by provider |
| 2. Collections | Net collection rate against allowed amounts | Which payer contracts and service lines to work | Payment and adjustment posting |
| 3. Ageing | A/R over 90 days as a share of billed A/R | Which accounts get worked and which get written off | A/R aging by payer |
| 4. Denials | Initial denial rate, plus denied dollars written off | Which root cause gets a fix, and who owns it | Remittance posting and denial queue |
| 5. Front end | Clean claim rate or first-pass acceptance | Whether scrub edits, registration or training change | Clearinghouse rejection report |
None of the five needs a formula invented here. The published definitions, with the inclusions and exclusions that make each number reproducible, sit in our reference on revenue cycle KPIs.
A sixth number earns its place only if it changes a decision the five cannot. Cost to collect, charge lag and credit balances fail that test at owner level, so they stay with the billing manager.
Why these five and not fifteen
Five is a limit, not a preference. The set covers the money, the backlog and the leakage without two lines measuring the same failure. Volume sits underneath the other four as the denominator. Collections and front-end quality cover what the payer owed and what got through clean. Ageing covers the backlog, and denials cover the leakage already visible on the remittance.
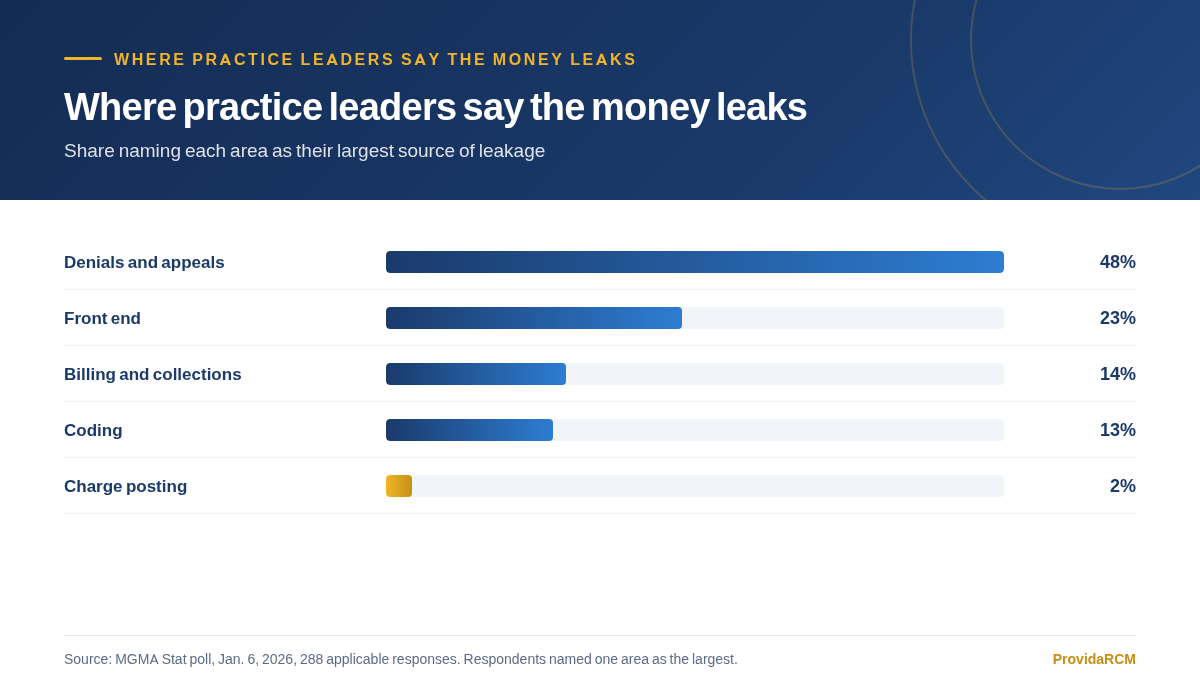
Practice leaders put the leaks where this set points. In a January 6, 2026, MGMA Stat poll of 288 medical groups, 48% named denials and appeals their largest source of revenue cycle leakage, 23% front-end issues, 14% billing and collections, 13% coding and 2% charge posting (MGMA Stat, detecting and fixing leaks).
The overlap test is simple. Two lines that always move together are one line carrying extra work. Volume and charges separate when the charge master changes, and clean claim rate moves a month before the denial rate does.
- Volume falls while collections hold: the practice does less work for the same money, and the decision is capacity, not collections.
- Clean claim rate falls and the denial rate has not moved: the front end broke this month, and the denials arrive next month.
- A/R over 90 days grows while collections hold: the practice is collecting the easy money and building a write-off out of sight.
Where each number comes from, and when it is true
A number is reportable when the report behind it can be named, the period it covers can be stated, and everybody agrees the posting has finished. Those three things turn a figure into something an owner can act on.
| Number | Source report | Period it covers | What has to be posted before it is true |
|---|---|---|---|
| Volume | Charge summary by provider | The calendar month, counted from date of service | Every completed encounter charged, including the last clinic day |
| Collections | Payment and adjustment posting | Payments received in the month | All remittances posted and unapplied cash matched |
| Ageing | A/R aging by payer and financial class | Balance as of the last calendar day | Late charges and corrected claims posted |
| Denials | Remittance posting and the denial queue | First denials posted in the month, once per claim | Remittances posted through the last business day |
| Front end | Clearinghouse rejection report | Claims submitted in the month | Every claim submitted, including resubmissions |
The cutoff is where reports quietly go wrong. A page pulled on the third, before the last remittances are posted, shows ageing too high and collections too low every time. Unmatched cash does the opposite damage, flattering collections and then moving the money later. Unapplied payments are the usual cause.
HFMA makes the same demand in writing. The MAP Keys name a preferred data source for each key, and the guidance is explicit that unless the processing system changes, the same sources must be used every month (HFMA MAP Keys).
The ageing line needs its population stated, because insurance balances and patient balances age at different speeds and get worked by different people. One ageing figure hides which side moved, and a payer-level split takes a few minutes to add to the same report.
Freeze the definition before the first report runs
A trend only means something when the thing being measured has not moved. Change the ageing definition in month four to include credit balances and the owner sees a line that broke and recovered with no change in the work. Freeze the definitions first, in writing.
One page is enough, one line per number, carrying the numerator, the denominator, the inclusions, the exclusions, the source report, the period and the posting cutoff. The owner and the billing manager both sign the version, which carries the date it took effect.
- Numerator and denominator in words: payments received divided by allowed amounts for the same service month.
- Inclusions and exclusions written out, including whether patient balances, credit balances and rebills sit inside the number.
- The exact name of the source report inside the system, so two people pull the same file.
- The posting cutoff as a date and a time, and the person who confirms it has passed.
- The version date, so a definition change is visible rather than remembered.
Attribution belongs on the sheet too. HFMA owns the definitions of the standard metrics and publishes no numeric target beside them, so a percentage described as an HFMA target is misattributed. The familiar 95% net collection floor and 30 to 40 days in A/R are AAFP five key metrics figures relayed by HFMA (HFMA KPI roundup).
The denial line also needs its code list named, because retired codes still circulate. CARC 16, a claim lacking information or carrying a billing error, is current and requires a remark code. CARC 29, the filing limit expired, is current. CARC 15 was deactivated on 1 May 2018, and the live code for an absent authorization is CARC 197 (X12 code list).
A clean claim rate of 95% called best in class, and a first-submission denial rate quoted for primary care, both circulate with no named survey, sample, year or dataset. If the publisher, the population and the date cannot be named, the line gets left off.
One page, thirteen months, the comparison that is honest
The page looks the same every month: five rows, same order, same labels. Each row carries the month, the prior month, the same month a year earlier and a thirteen-month strip beside it, so a reader sees whether something changed or wobbled.
Thirteen months rather than twelve, because thirteen covers a full prior year plus the month in hand. Seasonality stays visible, a January deductible reset does not read as a collapse in collections, and a fee schedule change from last summer is still on the chart.
Where days in A/R moved over the year, share of medical group leaders
Source: MGMA Stat poll, July 28, 2026, 203 applicable responses, reported July 30, 2026. Share of respondents.
| Compare against | What it answers | What it cannot answer |
|---|---|---|
| Your own last thirteen months | Whether this month is a change or ordinary movement | Whether the level would be better with a different payer mix |
| The same payer, same period | Whether a delay or denial pattern came from that payer | Whether the practice billed the claim correctly |
| Provider against provider, in your practice | Where documentation, coding or charge close differs | Why panel size and case mix differ |
| A published benchmark | Only what that publisher measured, in that population and year | Whether your specialty and contracts make you comparable |
Benchmarks belong in the meeting notes, not at the top of the page. The 30 to 40 day days in A/R figure is AAFP’s physician practice number relayed by HFMA, MGMA sells its medians inside subscription reports, and a per-specialty threshold with no named owner is folklore. The full argument is in days in A/R benchmarks.
What the page must not carry: a target the practice never set, a column labelled best in class, or a red and green status on a number whose definition nobody wrote down.
The meeting: who is in the room, and what gets decided
The meeting runs thirty minutes on the same business day each month, after the posting cutoff passes. The agenda is the page, in order, and nothing gets added unless a decision on the page requires it.
| Seated | Accountable for | What they bring | The decision they own |
|---|---|---|---|
| Owner or administrator | The page and the decisions taken from it | The margin and capacity questions | Whether capacity, staffing or a payer conversation changes this quarter |
| Billing manager | Collections, ageing and denial work | The source reports and the current work queue | Which accounts get worked and which get written off |
| Patient access lead | Eligibility, registration and point of service collection | The rejection report and the errors behind it | Which registration step changes before the next schedule |
| Coder or coding lead | Coding accuracy and documentation quality | Denial reasons by code and by provider | Which code family gets an audit and a teaching note |
| One clinician | Documentation and charge close | Note turnaround and the encounters still open | Whether a documentation standard changes this month |
Every line that moved becomes a decision, and every decision gets a name and a date. That conversion is the part practices skip.
- 01
Read last month’s decisions first
Open with the items that were due and say which closed. An item that survives two meetings is a staffing problem or a decision nobody agreed to.
- 02
State the decision, not the metric
The line that moved is not the agenda item. A/R over 90 days rising four points with one payer is, because it names work and a date.
- 03
Name one owner and one date
A decision with two owners has none. Write the person, the due date and the evidence that will show it worked.
- 04
Record it in the same place every month
One page of decisions, carried forward in the same file, so next month starts from a decision rather than a discussion.
The clinician seat is the one most often dropped from a billing review and the one that changes behaviour fastest. Provider-level denial patterns stop being an argument about the billing company.
The report that changes nothing
The failure mode is easy to describe and common to sit in. The page arrives on time, it is accurate, the room agrees with all of it, and nobody leaves with a task. Twelve months later the five lines sit at the same levels.
Three symptoms show it. The same line gets discussed every month and still has no owner. The meeting reviews the level rather than the change. The report improves while the work behind the numbers stays where it was.
One question tests the whole system. Can you name the last decision this report produced, the person who owns it and the date it was due? If the answer needs a search through email, the page is decoration.
Ageing and denial movement feed A/R management and denial management, and the front-end line feeds registration, eligibility and the scrub edits before a claim leaves. A practice that wants the page built with each line defined can start with our revenue cycle health check.
A page that produces one decision a month produces twelve a year. Few practices can point to twelve process decisions.
Questions practices ask us about this
What should a practice owner actually read in a monthly financial report?
Five lines: encounters and charges, net collection rate, A/R over 90 days, initial denial rate with denied dollars written off, and clean claim rate or first-pass acceptance. Those five cover volume, the money, the backlog and the leakage without overlapping. The decision each line drives matters more than the level.
How is a monthly owner report different from a revenue cycle KPI list?
A KPI list is a reference. It fixes formulas, inclusions and exclusions so two practices compare the same thing, which is what our published revenue cycle KPIs reference does. The owner report takes five of those metrics, freezes the definitions, and puts thirteen months on one page with a meeting attached.
Why thirteen months of trend instead of twelve?
Thirteen months covers a full prior year plus the month in hand, so every month has a same-month comparison from the year before. Seasonality stays visible, a January deductible reset does not read as a collapse in collections, and a fee schedule change from last summer is still on the chart.
Should a practice compare its numbers to a published benchmark?
Only when the publisher, the population and the date can all be named, and only as a third check. The honest comparisons are your own thirteen months, the same payer over the same periods, and provider against provider. The 30 to 40 day days in A/R figure is AAFP’s physician practice number, relayed by HFMA.
What has to be posted before the monthly numbers are true?
All electronic remittances for the month, including those arriving in the first week after month end. Unapplied cash has to be matched, because unmatched payments flatter collections and move the money in a later month. Charges for the last clinic day need posting, corrected claims need to land, and the aging report is pulled after the last calendar day.
How does the monthly meeting turn a number into a decision?
By opening with last month’s decisions, stating the decision each moved line calls for rather than the metric, and writing one owner and one due date per decision before the room breaks. Carry that page forward, and next month starts from a decision rather than the same five lines.
Want this fixed in your practice?
We run full-cycle billing, coding, credentialing and denial work for practices across the country. Send us a few months of claims and we will show you where the money is going.
Book a free billing review- HFMA MAP Keys, definitions with inclusions, exclusions and preferred data sources. hfma.org/data-and-insights/map-initiative/map-keys
- HFMA, Indicators of Revenue Cycle Excellence, 2023 Edition MAP Keys (PDF). hfma.org/wp-content/uploads/2023/10/2023-Edition-MAP-Keys.pdf
- HFMA, 7 KPIs providers should be tracking. hfma.org/revenue-cycle/kpis/7-kpis-providers-should-be-tracking
- HFMA Claim Integrity Task Force, Standardizing denial metrics for revenue cycle benchmarking. hfma.org/guidance/standardizing-denial-metrics-revenue-cycle-benchmarking-process-improvement
- MGMA Stat, Detecting and fixing leaks across the revenue cycle, January 6, 2026. mgma.com/mgma-stat/detecting-and-fixing-leaks-across-the-revenue-cycle
- MGMA Stat, Days in A/R holds steady for most practices, July 30, 2026. mgma.com/mgma-stat/days-in-a/r-holds-steady-for-most-practices-but-payer-pressure-persists-in-2026
- MGMA Stat, Operating costs keep climbing for medical practices in 2026, June 23, 2026. mgma.com/mgma-stat/operating-costs-keep-climbing-for-medical-practices-in-2026
- X12, Claim Adjustment Reason Codes (current list). x12.org/codes/claim-adjustment-reason-codes


